分类: health

  • The causes behind the causes

    The causes behind the causes

    By Dr. Ishma Harford, a medical doctor and Commonwealth Scholar pursuing a master’s degree in Health Analysis, Policy and Management

    Public health initiatives designed to address widespread population stress often start with bold, transformative goals. A holistic systems framework makes clear that most drivers of individual stress stem from factors outside a person’s personal control, requiring coordinated, society-wide solutions to resolve. These structural contributors range from systemic poverty and unequal access to life-saving medications and care services to deeply ingrained harmful cultural practices, among a host of other upstream issues.

    But what actually plays out in practice tells a different story: broad systemic action is abandoned entirely, and individual patients are left with nothing more than generic advice to improve their personal stress management. Public health discourse opens with robust discussion of overarching root causes, but when care reaches the frontlines, patients are simply told to make “healthier personal choices” to cope with their stress.

    Poverty stands as one of the most well-documented upstream drivers of poor population health. When an individual cannot cover their basic living expenses, they are forced to make impossible trade-offs that put their long-term health at risk: Should they pay to send their child to school, or use what little money they have to see a doctor about persistent, debilitating headaches? While it may be tempting to draw a simple direct line between poverty and avoidance of necessary care, this framing is a damaging over-simplification that erases the complex chain of systemic causes.

    To understand why low-income people forgo care, we must look past individual choice. This person chooses to prioritize their child’s education over investigating their own health symptoms because that is their only viable option when resources are stretched too thin. But why do they lack sufficient financial resources in the first place? If they are self-employed, it may be that their business is experiencing a prolonged slump. If they work as a local vendor serving the tourism industry, that slump could stem from an unexpectedly quiet tourist season that is entirely outside of their control. This chain of causation stretches on, with each link connected to broader structural conditions that one person cannot fix alone.

    Leading public health researcher Michael Marmot famously termed these interconnected systemic triggers “the causes behind the causes.” Public health even has formal analytical frameworks, such as root-cause analysis, designed to trace how these systemic factors ripple out to harm individual health outcomes.

    The harsh reality is that telling a patient to manage their own stress is far simpler and cheaper than addressing the structural issues that created that stress in the first place – like boosting a struggling local tourism economy to lift vendor incomes. A weak tourism season does not just harm one worker, either: a single systemic gap can leave hundreds of Grenadians dealing with unmanageable chronic stress.

    This gap between ambition and practice – where public health policy is meant to resolve deep-rooted systemic issues, but ultimately shifts responsibility for those problems onto the individuals they harm – is a well-documented phenomenon called lifestyle drift.

    Lifestyle drift is a quiet, easily overlooked failure of public health systems. Asking vulnerable people to cope with harmful conditions is always cheaper and politically easier than repairing the systemic conditions, such as poverty, that erode well-being and cause chronic stress. But ease does not equal effectiveness. When we shift a societal problem onto the shoulders of the individual people it harms most, we do not actually solve the problem – we just pass it down the chain, onto the shoulders of the most vulnerable members of our communities.

    Acknowledging this failure is a hard truth to accept. Many of these deep upstream problems cannot be resolved by public health authorities alone. A nation’s Ministry of Health cannot single-handedly end systemic poverty. Meaningful progress requires massive cross-sector collaboration between ministries of finance, all levels of government, and civil society across the entire country. Finding solutions requires making difficult, unpopular political decisions that carry short-term costs. But that does not mean we can avoid doing the work.

    So the next time you receive generic advice to just “manage your stress better,” it is worth asking the harder, more important questions: Are the causes of my stress actually fully within my personal control? And who is addressing the causes behind the causes?

    This article is part of *The Health Imperative*, a non-partisan educational column focused on health, health systems, and their broader societal impacts. NOW Grenada holds no responsibility for the opinions and statements shared by contributing writers. To report potential abusive content, please use the official reporting channel on the outlet’s website.


  • Miljoenenschuld zet gezondheidszorg in het binnenland op scherp

    Miljoenenschuld zet gezondheidszorg in het binnenland op scherp

    A leading healthcare provider delivering critical primary medical services to Suriname’s remote interior regions is sliding into an increasingly dire financial crisis, with unpaid government funds triggering cascading disruptions to care for thousands of vulnerable residents, multiple organization insiders have confirmed.

    De Medische Zending Health Care Suriname (MZPHCS), which operates under contract from the Suriname Ministry of Public Health to run primary care services across the country’s under-served inland areas, has not received any operational funding allocations for the 2026 service year, even as the year enters its third quarter. Unpaid outstanding debts have now climbed to millions of Surinamese dollars, and the mounting crisis is already directly impacting access to medical support in isolated communities.

    The most immediate and dangerous impact comes from disrupted air transport, a service MZPHCS relies on completely to respond to medical emergencies, restock critical supplies, and transport clinical staff to remote inland sites. With payment arrears reaching unsustainable levels, several commercial air carriers have already cut off services to the organization. Even Mission Aviation Fellowship (MAF), the non-profit aviation group that specifically operates in Suriname to support medical outreach and community development, has flagged its concerns over MZPHCS’s unpaid bills, according to Rachel Ten-A-Sang-Beerensteyn, MZPHCS’s Deputy Director for Finance, Facilities and Logistics.

    “Due to our massive outstanding payment backlogs, we can no longer access services from certain airlines,” Ten-A-Sang-Beerensteyn explained in an interview.

    Access to life-saving medications is also under growing strain. While the Suriname government took over a portion of MZPHCS’s outstanding debt to the national State Pharmaceutical Supply Company (BGVS), BGVS does not stock all the medications the organization needs to serve its patient population. This forces MZPHCS to source missing drugs from private suppliers, where it has now also accumulated unpaid balances, further limiting access to essential treatments.

    The financial shortfall has also left the organization’s care infrastructure crumbling across its 58 outpatient clinics spread across the interior. Every single facility requires maintenance of varying degrees of urgency, and some sites have dangerous, unaddressed defects: the delivery room at the Klaaskreek outpatient clinic is missing its entire ceiling, and the pediatric check-up room at the same facility has broken, non-functional windows that cannot be repaired.

    “Our staff are working around the clock to keep our clinics operational,” Ten-A-Sang-Beerensteyn said. “With the extremely limited budget we have available, we can only cover the most minimal, critical repair work. But that is nowhere near enough to address the backlog.” While MZPHCS partners with a range of local and international development organizations, these groups can only provide limited infrastructure support, as capital improvements do not align with their core program mandates.

    MZPHCS’s funding model, which combines contributions from registered insured patients, private donations, and project-specific grants, has long suffered from structural gaps that fail to cover full operational costs, even in non-crisis years. The 2026 funding delay has only worsened this chronic instability. “We are already in the third quarter of 2026, and we have still not received any operational funds for this service year,” Ten-A-Sang-Beerensteyn noted. Chronic delays in government disbursements create recurring funding gaps that force the organization to constantly improvise to keep services running. As an example, she explained that logistics staff must now repeatedly contact airlines on an ad-hoc basis to beg for space to ship essential supplies to care sites, an unstable system that cannot guarantee timely deliveries.

    While the Ministry of Public Health, Welfare and Labor (VWA) has stepped in on multiple occasions to provide ad-hoc relief to address MZPHCS’s immediate financial shortfalls, no long-term structural solution has been implemented to date. As a non-governmental organization contracted to advance the government’s own primary care access goals for the interior, MZPHCS leadership is now calling for permanent, structured dialogue between organization leadership, the Ministry of Public Health, and the Ministry of Finance and Planning to resolve the crisis.

    Ten-A-Sang-Beerensteyn emphasized that this dialogue would allow MZPHCS to share on-the-ground insights into the actual costs of delivering care to remote areas, and address a widespread lack of understanding among policymakers and the general public about the unique financial challenges inland care provision creates. “Structured dialogue can help build a better understanding of the daily financial reality we face,” she said.

  • Bordelais inmates get dedicated medical unit

    Bordelais inmates get dedicated medical unit

    A landmark new on-site medical unit has officially launched at Saint Lucia’s Bordelais Correctional Facility, bringing comprehensive, accessible healthcare services to nearly 560 incarcerated people who have long faced gaps in timely, professional medical support behind bars. The purpose-built facility offers a full spectrum of care, ranging from routine primary health services and emergency medical response to long-term chronic disease management and targeted mental health support, addressing a broad range of health needs that match those of the general public.

    The opening ceremony was led by two top government officials: Health Minister Moses Jn Baptiste and Minister for Crime Prevention Jeremiah Norbert, marking a collaborative cross-agency effort to improve correctional health outcomes. Moving forward, the Ministry of Health, Wellness and Nutrition will take full ownership of the unit’s operations, administration, and staffing—a structural change that public health and correctional leaders expect to transform healthcare delivery for the prison population while easing strain on the island’s overstretched public hospital system.

    Speaking at the launch last week, Jn Baptiste framed the new unit as far more than an infrastructure improvement: it is a core public, legal, and ethical obligation. “With close to 560 incarcerated residents, in addition to the facility’s full staff complement, we can fairly describe Bordelais Correctional Facility as a small self-contained community,” he explained. “That means guaranteed access to medical services here is not optional. It is a public health imperative, a legal imperative, and an ethical imperative.”

    Jn Baptiste emphasized that incarcerated people face the same widespread health challenges as the broader Saint Lucian population, from hypertension and diabetes to mental health disorders and infectious diseases. Expanding on-site access to consistent, evidence-based treatment does more than uphold the human rights of incarcerated people: it also cuts unnecessary costs for the national health system and strengthens Saint Lucia’s overall public health security by preventing unaddressed health issues from spreading beyond prison walls.

    Kerwin Albert, Director of Corrections, noted that consistent, timely access to qualified medical care has been one of the facility’s most persistent long-term challenges. By integrating the new unit into the Ministry of Health’s existing infrastructure, incarcerated people will now receive care from fully credentialed health professionals, with care protocols aligned to national public health standards. “This partnership between corrections and public health strengthens accountability, drives better clinical outcomes for patients, and reduces the unnecessary burden on our public acute care hospitals,” Albert said. He added that the initiative also reinforces a core principle: healthcare is a universal human right, even for people in custody, and supporting good health is a foundational part of successful offender rehabilitation.

    Prime Minister Philip J. Pierre also highlighted the new medical unit as part of a broader government push to improve conditions at the Bordelais facility. While his administration has already delivered tangible upgrades to working and living conditions for inmates and staff, Pierre acknowledged that additional improvements are still needed. He made clear that the government’s people-centered policy agenda extends to all Saint Lucians—including those serving sentences at the correctional facility.

  • Beperking tot 30 geneeskundestudenten maakt opleiding per arts fors duurder

    Beperking tot 30 geneeskundestudenten maakt opleiding per arts fors duurder

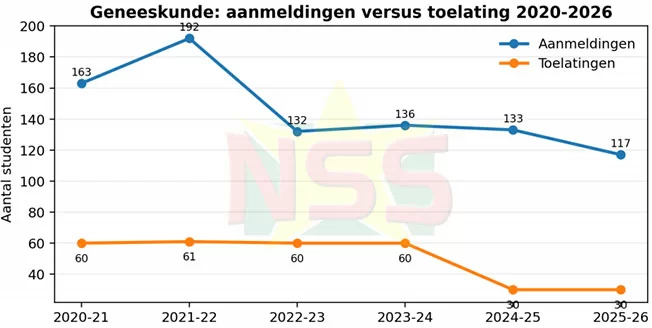
    On September 7, as Suriname’s Faculty of Medical Sciences (FMeW) welcomed its latest cohort of just 30 medical students, a landmark new study has laid bare the steep unintended consequences of the country’s annual intake cap for medical training. The analysis, compiled by a cross-functional team of leading medical education and healthcare experts, warns that holding student numbers at the current capped level drastically inflates the cost of training each new general practitioner, while unplanned expansion without infrastructure upgrades risks eroding training quality.

    The study was developed by FMeW Dean Fitzgerald Gopie, Vincent Lumsden (chair of the Suriname Specialists Registration Committee), and former Suriname Zorgfonds (SZF) director Rick Kromodihardjo, covering every stage of medical workforce planning from undergraduate admission to specialist training and national healthcare demand. Gopie led analysis of undergraduate metrics including intake rates, graduation outcomes, dropout rates, clinical clerkship placements and faculty quality, while Lumsden focused on postgraduate specialist training, registration requirements, trainee physician capacity and future specialist workforce projections. Kromodihardjo connected these training metrics to national healthcare needs, funding frameworks, labor market dynamics, regional distribution of medical professionals and long-term workforce planning.

    FMeW’s cost analysis draws on data from the 2020-2025 period, when the faculty admitted an average of just over 50 students annually. In that period, the median estimated systemic training cost per graduating general practitioner came out to roughly 4.6 million Surinamese dollars (SRD). With annual intake now capped at a permanent 30 students, fixed operational costs for the faculty and clinical training programs remain largely unchanged. As a result, the median estimated cost per graduating doctor will jump to as much as 7.7 million SRD, the analysis finds.

    The research team also modeled an alternative growth scenario: if the faculty scales intake in a controlled way to 60 students per year, the median cost per graduate would drop to approximately 3.9 million SRD. However, this cost reduction comes with a non-negotiable condition: training capacity – including numbers of teaching staff, lab facilities, clinical clerkship positions and quality monitoring infrastructure – must expand in lockstep with higher intake. The study thus warns against two problematic extremes: permanently low intake that makes each medical degree prohibitively expensive, and unregulated expansion that amplifies bottlenecks later in the training pipeline.

    A key conceptual distinction the FMeW draws in the study is between two separate intake policy frameworks: Numerus Fixus and Numerus Clausus. Numerus Fixus sets an annual intake target based on the total number of physicians Suriname needs to meet national healthcare demand. Numerus Clausus, by contrast, sets a limit based on how many students the university can responsibly train given existing constraints on staff, facilities and clinical placement capacity. The study argues that these two figures must be calculated separately each year before being aligned, rather than automatically equating national workforce demand with current available training capacity.

    Between the 2020-2021 and 2025-2026 academic years, a total of 873 candidates applied to the FMeW medical program, and 301 were admitted. In recent years, the formal annual intake cap has been cut to 30 students, creating a pressing policy challenge that the study aims to address. FMeW officials emphasize that current intake restrictions are not arbitrary: the entire training chain faces objective capacity limits, from available clinical clerkship positions and faculty supervision to lab space, historical graduation rates and overall clinical infrastructure. At the same time, the faculty warns that capping admission is not a standalone solution to the country’s future physician supply challenges.

    One of the most critical bottlenecks currently sits further along the training pathway, not at admission. The study records that FMeW only has between 30 and 40 active clinical clerkship positions available, yet there are already 79 current clerkship students and an additional 24 students waiting for placements. More cohorts of students are progressing toward the clinical phase of training every year. The research team explains that admitting more students without expanding clinical capacity would only shift the bottleneck, leading to longer wait times for clerkships and increased pressure that undermines training quality.

    The study’s core policy recommendation calls for a coordinated, holistic approach to medical workforce planning in Suriname. Rather than only deciding on annual admission numbers, the country must first clarify how many physicians it actually needs to meet population healthcare needs, and calculate what targeted investments are required to train that workforce responsibly. Researchers advise that policymakers re-evaluate the alignment between Numerus Fixus (demand-based targets) and Numerus Clausus (capacity-based limits) every year, and tie any increase in admission quotas directly to additional investment in teaching staff, clinical training placements, supervision and quality assurance systems.

  • Health Ministry targets gaps in health system

    Health Ministry targets gaps in health system

    A 2022 comprehensive assessment of Barbados’ national health system has exposed critical shortcomings in digital infrastructure and organization, pushing the Caribbean nation to accelerate its digital transformation efforts to elevate patient care standards, according to a top health ministry official.

    Stacie Goring, Acting Director of the Planning and Research Unit at Barbados’ Ministry of Health, outlined these findings and the way forward during a recent virtual public consultation focused on the digital element of the country’s Health Services Resilience Programme. Goring explained that the evaluation uncovered a deeply fragmented health information ecosystem, marked by severely limited interoperability and weak data sharing across the nation’s core healthcare facilities. Major care providers including the Queen Elizabeth Hospital (QEH), community polyclinics, diagnostic laboratories, and retail pharmacies currently operate disconnected digital systems that prevent seamless information flow between care settings.

    Beyond fragmented infrastructure, the assessment flagged multiple additional gaps that demand urgent attention. These include incomplete policy frameworks and inconsistent industry standards, persistent challenges with data accuracy and consistent reporting, underdeveloped core digital infrastructure, and unreliable connectivity in many care facilities. Goring also noted that Barbados currently lacks sufficient trained capacity in digital health and health informatics, and needs to implement stronger safeguards to protect patient data privacy and prevent cybersecurity breaches.

    Despite these well-documented shortcomings, Goring emphasized that Barbados has already made meaningful progress in rolling out digital health initiatives across its entire care continuum. In the primary care sector, all polyclinics currently use an electronic medical record system that covers core administrative and clinical functions, from patient registration and appointment scheduling to admission management and centralized digital health record storage. These facilities also leverage digital tools to power public health surveillance, infectious disease testing, and ongoing patient monitoring.

    At the QEH, the island’s main tertiary care facility, a large-scale modernization project is already underway. The centerpiece of this work is the deployment of a fully integrated enterprise health information system, alongside a full digitization project converting all existing paper patient and medical records to digital formats. The project also includes major investments in core information and communications technology (ICT) infrastructure, including new servers, clinician workstations, and mobile tablets that will give care teams instant access to unified patient records across every hospital department. Goring projected that the full shift to electronic medical records will cut down on the longstanding problem of lost patient files, improve clinical decision-making and patient outcomes, and streamline end-to-end hospital workflows.

    Work is also progressing to upgrade digital capabilities at the Best-dos Santos Public Health Laboratory, the nation’s leading public health testing facility. Upgrades there include a modernized laboratory information management system that will fully integrate lab test results into centralized patient electronic health records, eliminating delays and information gaps for clinicians. At the country’s public pharmacies, electronic prescribing and medication tracking systems are already in operation, giving clinicians instant visibility into a patient’s full medication history to reduce adverse drug interactions and improve overall patient safety.

    Officials are also conducting a full review of existing national legislation to determine whether current laws provide adequate regulatory support for electronic health records and digital care delivery, a key step to formalize the transformation process.

    In closing, Goring stressed that sustainable digital transformation in health requires far more than just investing in new hardware and software. “Moving forward, one of the critical things we want to emphasise is that digital health is more than technology. It’s about governance and management. It’s about people and culture, infrastructure, a set of services and applications, and informed health policy and practice,” she said.

  • Freeport Health Campus now 30 percent complete

    Freeport Health Campus now 30 percent complete

    On a Friday site visit led by Bahamas Prime Minister Philip “Brave” Davis and Health and Wellness Minister Dr Michael Darville, top government officials confirmed that the long-awaited Freeport Health Campus project is back on track and currently 30% complete, with substantial finishing of the facility’s first phase scheduled for July 2027.\n\nJoined by Minister for Grand Bahama Ginger Moxey, West Grand Bahama MP Kingsley Smith, and senior hospital and project management officials, the tour revealed that construction work has fully restarted after the government secured critical financing via a loan from CIBC. The 80,000-square-foot first phase facility, being built by general contractor ABC Construction with Veritas Consultants Limited acting as owner’s representative and project agent for the Public Hospitals Authority, has expanded significantly from its original 62,000-square-foot design. Nearly 18,000 square feet of additional space has been added to the facility’s basement, a modification that will serve two key community needs: a designated hurricane shelter and a new training hub for the Public Hospitals Authority Academy.\n\nDr Darville outlined the current construction timeline, noting that crews are now pouring the facility’s main roof slab. Once this step is complete and the entire building envelope is sealed, internal construction work will commence. The government remains committed to opening the first phase by the end of 2027, with full commissioning expected no later than September of that year, according to John Michael Clark, president and managing director of Veritas Consultants. Clark added that all foundational work and the main building superstructure are already in place, and construction has also begun on the campus’s Central Utility Plant, a critical infrastructure component for the facility’s long-term operation.\n\nLooking ahead to the project’s second phase, Dr Darville confirmed that design work for the planned multi-story inpatient tower – which will house the majority of the new hospital’s patient beds – is nearly complete. Lead architects and structural engineers The Beck Group have finished the bulk of the design, and the government will launch a public tender bidding process for the second phase construction in the near future.\n\nPrime Minister Davis praised the project team for advancing the development after previous setbacks that caused significant delays. He noted that the additional hurricane shelter space holds particular resonance this week, as the nation marks the seventh anniversary of Hurricane Dorian, the devastating storm that exposed critical gaps in emergency safe shelter infrastructure across Grand Bahama. “To see that you will now have somewhere where people feel safer than they were then is also what I say is a sign of progress for us,” Davis said during a press briefing after the tour.\n\nBoth Davis and Dr Darville emphasized that the new health campus is being built to meet both current and future demand for healthcare on Grand Bahama, where the existing Rand Memorial Hospital has operated beyond its maximum capacity for 15 to 20 years. Davis framed the $project as a forward-thinking investment aligned with projected economic and population growth across the island, saying “we expect Grand Bahama to be thriving in a way that this hospital will be able to accommodate that exponential growth in the economy that we have here.” Dr Darville added that the Freeport Health Campus will become the new hub of tertiary healthcare for Grand Bahama, designed to serve generations of residents as the island develops.

  • Seniors urged to guard against heat

    Seniors urged to guard against heat

    As record-breaking high temperatures and persistent dry conditions push the risk of heat-related illnesses sharply higher across Barbados, public health and senior advocacy leaders are sounding the alarm for the island nation’s older population to prioritize safety amid the extended heatwave. Meteorological authorities confirmed in an updated official weather bulletin that unusually hot conditions will remain locked in across the entire country through September and October, bringing repeated stretches of dangerous heat that require proactive precautions from all residents, especially vulnerable groups. With forecasters warning of elevated threats ranging from heat exhaustion and rapid dehydration to life-threatening heat stroke and sudden fainting, Marilyn Rice-Bowen, president of the Barbados Association of Retired Persons (BARP), has stepped up outreach to encourage older adults and their family members to take the ongoing heat emergency seriously. Speaking in an interview with Barbados TODAY, Rice-Bowen noted that while hot, sunny weather is a constant for the Caribbean nation, the current heat event poses unprecedented risks that cannot be overlooked. “For many of us, Barbados’ heat is nothing new. We have lived with hot days, strong sunshine and sometimes some uncomfortable nights. But what we are experiencing now is different,” she emphasized. Current air temperatures regularly hit 32°C to 33°C across the island, and apparent temperatures – which factor in humidity to measure how heat actually feels on the human body – often climb close to 45°C. This combination places extreme physiological strain on older bodies, Rice-Bowen explained, because aging reduces the body’s ability to regulate internal temperature efficiently. Older adults face a far higher risk of rapid dehydration, dizziness, fainting, heat exhaustion, and fatal heat stroke compared to younger populations, she added. To help seniors stay safe, BARP has released a full set of actionable guidelines tailored to older residents. Key recommendations include drinking water consistently throughout the day, even when a person does not feel thirsty, avoiding extended outdoor activity during the peak heat hours between mid-morning and late afternoon, and wearing loose-fitting, light-colored clothing that reflects sunlight. For those venturing outside, the association advises using wide-brimmed hats or sun umbrellas to block direct sun exposure. BARP also urges older adults to keep their living spaces cool and well-ventilated, using fans or air conditioning when available to lower indoor temperatures, and taking regular cool showers or baths to bring down core body temperature. Beyond individual precautions, Rice-Bowen is calling on community members to step up and support vulnerable older residents, particularly those who live alone. A quick daily check-in via a simple phone call or brief doorstep visit can make a life-saving difference for seniors who may struggle to recognize the early signs of heat illness, she said. Most critically, Rice-Bowen warned against dismissing early warning symptoms of heat-related sickness. Common red flags include confusion, persistent muscle weakness, dizziness, unexpected fainting, and severe headaches, and anyone experiencing these symptoms should seek immediate medical care, she stressed. The warning comes after Dr. Lynda Williams, president of the Barbados Association of Medical Practitioners (BAMP), confirmed earlier this month that local doctors are already seeing a sharp rise in heat-related illness among elderly patients who became sick while at home, underscoring the urgent need for proactive safety measures.

  • Bodoe: Only a few CDAP drugs affected by shortages

    Bodoe: Only a few CDAP drugs affected by shortages

    In a radio interview with I95.5 FM yesterday, Trinidad and Tobago’s Health Minister Dr Lackram Bodoe publicly addressed growing public complaints over drug shortages under the nation’s long-running Chronic Disease Assistance Programme (CDAP), confirming supply gaps for a small subset of medications while outlining immediate and long-term plans to resolve the issue.

    Established two decades ago, CDAP enables nearly 300,000 local citizens to access subsidized chronic disease medication through a network of 289 participating private pharmacies across the country. Out of the 52 prescription medicines officially listed on the programme’s formulary, Bodoe confirmed that only six to seven are currently out of stock, leaving between 43 and 45 medications fully available for patient pickup.

    Bodoe emphasized that the current shortages are not a permanent or funding-related crisis. He clarified that procurement logjams, rather than a lack of government allocation for health services, are the root cause of the temporary supply disruptions. The government allocates between $800 million and $900 million annually to cover public-sector medication costs, including CDAP supplies, so funding is not a constraining factor. The Minister projected that all out-of-stock drugs will be restocked and available to patients within three to four weeks, once ongoing procurement processes are completed.

    In the interim, Bodoe said that safe, clinically effective alternative medications are already available for all currently out-of-stock drugs. He has issued guidance to clinicians to prescribe these proven alternatives when a patient’s usual CDAP medication is unavailable, and that participating pharmacists are prepared to dispense the substitute treatments. For context, Bodoe cited the common hypertension drug Lisinopril, which is currently out of stock under CDAP, as an example: Enalapril, another effective hypertension treatment, is readily available as a replacement.

    Beyond addressing immediate CDAP shortages, the Minister revealed that the health ministry is undertaking a broader overhaul of national pharmaceutical management, including a full revision of the national formulary that sets priorities for state-funded drug purchases. The revision process involves input from practicing clinicians across the country to ensure public funds are allocated to the most clinically necessary and effective medications.

    This review extends to high-priority categories including cancer treatments, where Bodoe noted the ministry is working alongside national oncologists to evaluate purchasing priorities. He explained that with a constant stream of new oncology drugs entering the global market, the government has a responsibility to balance patient access with fiscal prudence: many new cancer treatments have not yet established clear long-term clinical efficacy, so public funds must be directed toward treatments with proven patient outcomes.

    In a surprising disclosure during the interview, Bodoe revealed that an internal supply chain audit covering 2016 through 2025 uncovered a far larger systemic issue: more than $300 million worth of publicly funded pharmaceuticals and medical supplies have expired while stored in the national public health supply system. The Minister stressed that at no point were these expired medications distributed to patients for use; all expired stock was properly disposed of before reaching clinical settings. Nonetheless, he described the accumulation of hundreds of millions of dollars in expired supplies as an unacceptable supply chain failure, and confirmed that the Ministry of Health and National Insurance Property Development Company (NIPDEC) are already collaborating to implement corrective measures to prevent this issue from recurring in the future.

  • There have been 19 deaths due to leptospirosis

    There have been 19 deaths due to leptospirosis

    Over the past week, national public health officials have updated the country’s epidemiological database with two new confirmed cases of leptospirosis, a zoonotic illness that spreads through contact with contaminated sources. As of the latest update from the Ministry of Public Health’s National Epidemiological Surveillance System (Sinave), the cumulative number of confirmed leptospirosis cases recorded since the start of the calendar year stands at 272, with at least 19 fatalities linked to the disease. Unlike many common communicable illnesses, leptospirosis is most often contracted through direct exposure to the urine of infected animals—particularly rodents—or by consuming water and food that has been contaminated by this bacteria. This means poor sanitation and unhygienic living environments significantly increase a community’s risk of an outbreak.

  • QEH expansion targets chronic lab, bed shortages

    QEH expansion targets chronic lab, bed shortages

    Barbados is poised to undertake a sweeping, multi-year modernization project for its primary public healthcare facility, the Queen Elizabeth Hospital (QEH), backed by $175 million in development bank financing. Senior Minister for Social and Environmental Policy Senator Dr. Jerome Walcott outlined the urgent needs and planned transformations during a recent community and stakeholder consultation focused on the QEH/Enmore redevelopment, a 42-month initiative that will reshape the island nation’s tertiary healthcare capacity over the next three to four years.

    For decades, QEH has grappled with systemic gaps that have compromised its ability to deliver high-quality care to Barbadian residents, Dr. Walcott revealed. Longstanding challenges include overcrowded inpatient areas, chronic bed shortages, outdated and undersized laboratory infrastructure, limited access to comprehensive cancer care, and a critical gap in specialized burn treatment – a gap that has already resulted in preventable deaths. Decades ago, the hospital operated a functional burn unit, but that service was discontinued, leaving the island without capacity to treat severe burn injuries locally. In the most recent four serious burn cases, all patients required emergency airlift to Panama for specialized care, and none survived, according to Dr. Walcott, a former practicing physician at QEH. He emphasized that a 21st-century tertiary hospital cannot credibly claim to serve the public without a dedicated burn unit, which provides specialized intensive care that is standard across North America and Europe. “When I was a doctor years ago at the hospital, there was a burns unit, and I believe as we go forward in the 21st century to speak of having a tertiary hospital and not having a burn unit, you’re making fun,” he said.

    The most neglected part of the current facility is the hospital’s laboratory, which has suffered from unresolvable mould infestation since before the COVID-19 pandemic. Years of targeted repairs, reconfigurations, repeated industrial cleaning, and in-house maintenance efforts by QEH’s engineering team have failed to eliminate the mould, creating unsafe working conditions for staff and compromising testing reliability. A 2020 independent assessment of the facility identified two potential solutions: reallocate existing space by moving other departments to expand the current lab, or construct an entirely new laboratory facility. Stakeholders have now finalized a decision to build a new, purpose-built lab, addressing the persistent safety and capacity issues.

    The redevelopment project, centered at the Enmore site, will add two new multi-story towers to the QEH campus. The first tower will house the upgraded outpatient department and the new state-of-the-art laboratory, while the second will be dedicated to oncology services and hospital administrative offices. For inpatient care, the project will add four entirely new wards with 96 additional beds to alleviate chronic overcrowding. Outpatient services will also be expanded to offer dedicated, separate space for specialized clinics including otolaryngology (ENT), neurology, and paediatrics, with new on-site equipment for EEG and EMG diagnostic testing.

    A core priority of the expansion is closing gaps in cancer care that currently force many patients to travel overseas for life-saving treatment. The project will add critical specialized oncology infrastructure including a new Positron Emission Tomography (PET) scanner, an updated Gamma CT scanner, and a dedicated brachytherapy facility. For the first time, Barbados will also acquire a cyclotron to produce its own radiopharmaceuticals – radioactive compounds used both for diagnostic imaging and targeted cancer treatment. Chemotherapy treatment capacity will also be scaled up, allowing the facility to treat 10 to 12 patients simultaneously, cutting wait times and reducing the need for off-island care.

    Dr. Walcott framed the $175 million transformation as a strategic investment that will strengthen the resilience of Barbados’ entire national health system. Beyond improving care for local residents, the project aims to restore Barbados’ historic role as the leading medical referral hub for complex cases across the Eastern Caribbean. The recent consultation is part of ongoing stakeholder engagement as the government prepares to launch construction and finalize project planning for the large-scale redevelopment.