
Processing difficult life events and gaining clarity about our own experiences is a challenge many people grapple with, but a growing body of narrative psychological practice points to a simple, accessible tool for healing: writing down your own life story.
分类: health
-
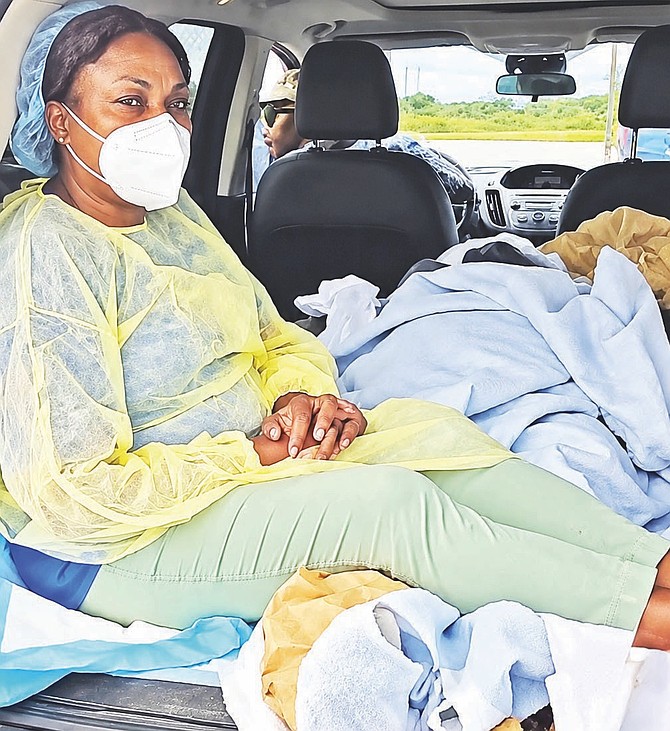
Nurse transports patient in jeep amid ambulance shortage
A disturbing video captured on the Bahamian island of Mangrove Cay has sent shockwaves across social media, laying bare a years-long crisis in pre-hospital emergency care for the country’s outlying Family Islands. The 24-second clip shows a nurse riding in the rear of a private jeep, with her legs stretched out over a patient who was en route to be airlifted to the main hospital hub on New Providence for urgent care. This incident is far from isolated, and it has reignited fierce criticism of the Bahamian government’s failure to address longstanding healthcare inequities between the capital region and smaller outlying islands.
Mangrove Cay, which is part of the larger Andros island chain, has been without a single operational ambulance for more than 10 years, according to local nurses who spoke with Bahamas Nurses Union president Muriel Lightbourn after the video went viral. Lightbourn issued a scathing rebuke of what she called the “deplorable” state of healthcare across the Family Islands, questioning not only the quality of care that patients are forced to accept but also the safety risks placed on frontline nursing staff. “If something were to happen to the nurse while she was traveling in that private vehicle, would she even be covered by worker’s protections?” Lightbourn asked in an interview, adding that it is “so wrong” that residents of these smaller islands have grown accustomed to substandard emergency care.
Bahamas’ Minister of Health and Wellness Dr. Michael Darville acknowledged the ministry’s awareness of the viral video and the long-running ambulance shortage on Mangrove Cay and other Family Islands. He confirmed that the central government has already earmarked ambulances for Mangrove Cay and other affected islands, and that the rollout of a revised emergency medical services (EMS) system across the Family Islands will be implemented in phases. The Cabinet has already approved the purchase of 10 to 12 new ambulances, Darville explained. Once these new vehicles arrive in the more populous islands of New Providence and Grand Bahama, currently allocated ambulances from those regions will be reallocated to meet the needs of smaller outlying islands like Mangrove Cay.
Darville pushed back against claims that the government has failed the Andros region, noting that three new, fully operational ambulances are already serving residents at clinics across North, Central, and South Andros, including the Miriam Green clinic. Transport Minister Leon Lundy, who also serves as the Member of Parliament for Mangrove Cay and South Andros, acknowledged that local residents have every right to be frustrated by the persistent lack of emergency services. He told reporters that a new ambulance is expected to be deployed to Mangrove Cay once construction on the island’s local clinic is completed, and pledged to continue advocating for the reliable emergency healthcare that local residents deserve.
This viral incident is only the latest in a string of high-profile cases that have exposed the deep gaps in emergency care across the Family Islands. In September 2025, a critically ill woman on Long Island had to be carried to an awaiting air ambulance on the back of a flatbed truck in heavy pouring rain – even though two fully functional ambulances were parked unused on the island. After that incident and a subsequent fatal crash that also exposed inadequate emergency transport, Darville publicly promised that such dangerous, undignified scenes would become a thing of the past, claiming the era of moving critically injured patients on the backs of trucks to reach air ambulance hubs was over.
-

Pay grieving mothers
A months-long legal battle over public transparency has reached a turning point, as top legal advocate Anand Ramlogan is pushing Trinidad and Tobago’s North West Regional Health Authority (NWRHA) to put an end to court proceedings and negotiate fair settlements with the families of seven newborns who died in a bacterial outbreak at Port of Spain General Hospital in April 2024.
Ramlogan made his appeal fresh off a landmark High Court decision this past Thursday, which ruled in favor of his client Shanya Raymond-Adams and ordered the NWRHA to release its internal investigative report into the preventable infant deaths. In a formal public statement, the senior counsel accused the public health authority of misappropriating taxpayer dollars to fend off the grieving families’ legal claims, rather than offering clear answers about what caused the outbreak and just compensation for their devastating loss.
“No amount of financial settlement can bring back the seven infants that these families lost, or heal the profound grief that their mothers have carried every day since,” Ramlogan said in his statement. “That said, fair settlement offers would provide meaningful support to these families and spare them the additional pain and stress of dragging this process through the courts for months or years to come.”
Ramlogan led the successful legal challenge against the NWRHA on behalf of Raymond-Adams, who was one of the mothers denied access to the internal authority’s internal probe findings after the outbreak. He condemned the authority’s months-long refusal to release the report as a blatant injustice, noting that grieving parents had been forced to sue the very public institution that was trusted to care for their infants just to learn how their children died.
He pointedly criticized the NWRHA for its treatment of the families, highlighting that more than two years after the outbreak, the affected mothers have not received any compensation while the authority has drained public funds on legal fees to delay the case. Ramlogan is also calling for formal accountability for the officials who made the decision to withhold the report, arguing that covering up findings from an investigation into preventable infant deaths can never be justified under any circumstances.
The case lays bare a stark contradiction between the NWRHA’s public commitments to transparency and its behind-the-scenes efforts to block disclosure, Ramlogan emphasized. Then-NWRHA chief executive officer Anthony Blake publicly promised just weeks after the 2024 outbreak that the full investigation findings would be released to the public. But just months later, Blake submitted a sworn court affidavit opposing Raymond-Adams’ request for the documents, backing the authority’s claim that the report was protected from disclosure under legal professional privilege.
In his ruling, Justice Robin Mohammed rejected that argument, finding that the NWRHA failed to produce sufficient documentation to prove the report qualified for privilege protection. Ramlogan called the authority’s broken promise of transparency blatant hypocrisy, noting that the grieving mothers reasonably trusted the NWRHA’s public commitment to openness as they navigated the loss of their children.
The court ruling, Ramlogan said, raises urgent new questions about why the NWRHA chose to wage a prolonged and expensive court battle instead of honoring its original promise to release the findings. He is now urging the authority to move quickly to comply with the court’s disclosure order, redacting only necessary confidential personal information before making the full report public.
“These families, and the entire country, have a right to know what the investigation uncovered: what led to these babies’ deaths, where systemic failures occurred, and what changes have already been implemented to stop this tragedy from happening again,” Ramlogan said. “These mothers have carried their grief and fought for answers for years. They have waited long enough, and the truth about these deaths can no longer be hidden.”
-

Judge slams NWRHA over newborn deaths
A landmark High Court ruling has delivered a sharp rebuke to Trinidad and Tobago’s North West Regional Health Authority (NWRHA), finding the public body improperly hid behind legal professional privilege to avoid releasing records related to the 2024 deaths of seven newborns at Port of Spain General Hospital, and failed to uphold its own mandatory investigation policies.
The tragedy unfolded in April 2024, when a bacterial outbreak swept through the hospital’s Neonatal Intensive Care Unit (NICU), claiming the lives of seven premature and vulnerable infants. Among the victims was Kae’ Jhene Kerniah Charles, born prematurely at 32 weeks to Shanya Raymond-Adams. The infant was admitted to the NICU immediately after birth, appeared initially stable, but developed a life-threatening blood infection and died just five days later, on April 6. Weeks after her death, Raymond-Adams learned via an NWRHA media statement that her daughter was one of seven babies who died in the outbreak between April 2 and 9.
Following the public outcry over the deaths, the NWRHA launched an internal investigation under its own Adverse Events Policy, with then-CEO Anthony Blake publicly promising full transparency and disclosure of the investigation’s findings. When Raymond-Adams filed a Freedom of Information Act (FOIA) request for the internal investigative report, witness statements, and the investigation’s terms of reference in July 2024, however, the NWRHA refused to release any records. The authority argued the documents were protected from disclosure by legal professional privilege, claiming the investigation had shifted to primarily preparing for expected litigation from bereaved families.
In a 65-page judgment delivered Thursday, Justice Robin Mohammed rejected the NWRHA’s claims entirely, ruling the authority’s refusal to disclose was illegal and breached the FOIA. Justice Mohammed found the NWRHA failed to produce any credible, contemporaneous evidence – including meeting minutes, file notes, or formal resolutions – to support its assertion that the investigation’s core purpose had changed from examining the outbreak to preparing legal defense. Without this supporting documentation, the judge ruled the authority’s reliance on privilege was “a construct of convenience” designed to evade its statutory transparency obligations.
The ruling also exposed critical failures in the NWRHA’s internal investigation itself. Justice Mohammed confirmed the authority failed to interview the bereaved mothers of the deceased infants, a direct violation of Section 12.6.3 of its own Adverse Events Policy, which explicitly requires investigators to collect statements from patients or their next of kin. The judge emphasized that even if the authority claimed the investigation was being conducted for legal purposes, this did not eliminate its statutory and internal policy obligation to conduct a full, impartial probe into the deaths. This failure to collect firsthand accounts from affected families, he found, amounted to a clear breach of the NWRHA’s own policies.
Justice Mohammed also addressed the NWRHA’s attempts to discredit an independent investigation conducted by a three-member team from the Pan American Health Organization (PAHO), which was presented to Trinidad and Tobago’s Parliament in June 2024. That report uncovered alarming systemic failures at the hospital: it found compliance with basic infection control standards was as low as 29%, documented chronic understaffing, and confirmed the hospital had no dedicated staff assigned to infection prevention and control. The NWRHA criticized the PAHO report’s findings, but Justice Mohammed ruled the authority produced no substantive evidence to undermine the independent assessment.
In his final analysis, Justice Mohammed noted that public interest in disclosure far outweighs the NWRHA’s claims to confidentiality. The internal report remains the only authoritative internal assessment of the outbreak, and bereaved families like Raymond-Adams are entirely dependent on the authority for information on whether systemic failures or medical lapses contributed to their children’s deaths. The judge added that the NWRHA’s ongoing lack of transparency, in the face of evidence of potential neglect, harm to vulnerable infants, and injustice to grieving families, has only compounded public anxiety over the incident.
Justice Mohammed quashed the NWRHA’s original decision to withhold the documents, ordered the authority to release all requested records to Raymond-Adams (with only limited, appropriate redactions if permitted), and ruled the NWRHA must pay all of Raymond-Adams’s legal costs for the judicial review challenge. Six other families of the deceased newborns have also filed separate legal action against the NWRHA, and Thursday’s ruling sets a critical precedent for their demands for transparency and accountability.
Senior Counsel Anand Ramlogan led the legal team representing Raymond-Adams, supported by attorneys Jayanti Lutchmedial, Kent Samlal, Jared Jagroo, Natasha Bisram and Aasha Ramlal. The NWRHA was represented by Senior Counsel Ravindra Nanga, Stephan Maharaj and Alana Bissessar.
-

Private sector calls for strict controls to block smuggling of vaping products
On October 18, 2026, two of Guyana’s leading business advocacy organizations have united to call on national authorities to crack down on illicit smuggling of vaping products, amid growing concerns over the severe public health threats these items pose to the country’s youth. The Guyana Manufacturing and Services Association (GMSA) and the Georgetown Chamber of Commerce and Industry (GCCI) both outlined a series of actionable recommendations to strengthen the country’s existing de facto ban on non-medical vaping products, ensuring the policy delivers on its intended public health goals.
As an affiliate of Guyana’s umbrella Private Sector Commission (PSC), the GMSA emphasized that firm, consistent enforcement at every port of entry into the country is non-negotiable to block unapproved shipments and prevent the emergence of an unregulated black market. The group also pushed for clear, transparent regulatory guidance that outlines import restrictions, formal approval and exemption processes, and a concrete timeline for full implementation. Currently, President Irfaan Ali has not yet specified when Finance Minister Dr Ashni Singh will issue the formal executive order under the Customs Act that will codify the ban.
Echoing the GMSA’s priorities, the GCCI stressed that strengthened border monitoring, clearly defined import and exemption protocols, and aggressive enforcement against unauthorized distribution are all critical components of an effective ban. “These measures will be essential to ensuring that the restrictions meaningfully reduce access to vaping products, particularly among young people, without creating opportunities for unregulated markets,” the GCCI stated in its official release. The chamber added that the long-term success of the vaping restrictions hinges on three core pillars: clear regulatory frameworks, uniform enforcement across all agencies, and ongoing constructive engagement with impacted businesses. It warned that unaddressed illicit trade would completely undermine the public health protections the policy aims to achieve.
The GMSA has already called on its own members, as well as the broader national business community, to fully comply with the new restrictions and back the government’s public health effort. “We stand ready to work with the government, health authorities and all stakeholders to safeguard the well-being of our children and the future of our nation,” the association said. Beyond enforcement, the GMSA recommended two additional key steps for authorities: proactive consultation with impacted import and retail businesses to allow for orderly compliance, and widespread public education campaigns rolled out in schools, households, and religious centers to raise awareness of vaping’s inherent health dangers.
The Private Sector Commission, the national umbrella body for private sector interests, echoed these calls, urging all importers, distributors, and retailers to adhere fully to the announced requirements. “Ensure that their sales and marketing practices do not encourage vaping among children and adolescents,” the PSC said, adding that “clear implementation guidance and cooperation between the authorities and the business community will be essential to achieving the intended protections.”
President Ali has previously outlined the broad health harms linked to vaping, noting that the practice can damage respiratory health, mental well-being, and reproductive health. Under the current policy framework, only the Minister of Health, the Tobacco Control Board, or the National Tobacco Control Council have the authority to approve imports of vaping products for limited medicinal or therapeutic purposes.
Concerns over illicit vaping trade are not unfounded: back in January 2026, the Customs Anti-Narcotics Unit (CANU) announced that its early warning detection system led to the seizure of multiple branded vape cartridges laced with high-potency THC, the psychoactive compound found in cannabis. CANU officials reported that the seized products were professionally packaged in bright, colorful designs explicitly targeted at young consumers, marking a worrying shift in the illicit drug trade toward high-potency cannabis concentrates disguised as mainstream consumer vaping products. The agency warned that these unregulated products pose severe public risks, including their extremely high THC content, unknown and potentially toxic contaminants, intentional appeal to youth, and their illegal status across Guyana.
-

Ministry of Health Congratulates Newly Appointed Midwifery Board Members Following Swearing-In Ceremony
In a formal ceremony held at Government House on Wednesday, 14 October 2026, Antigua and Barbuda’s newly appointed Midwifery Board members took their oaths of office, administered by Governor General His Excellency Sir Rodney Williams. The announcement of the new leadership panel was made official by the country’s Ministry of Health, Wellness, Environment and Civil Service Affairs.
Leading the newly formed board is Dr. Kamaria DeCastro, who has been named Chairperson. Taking on the role of Deputy Chairperson is experienced nurse Patricia-Ann Clarke-Thomas. The full roster of sitting board members includes five additional nursing professionals: Nurse Jacqueline Jno-Baptiste, Nurse Laurellyn Williams, Nurse Arlea Gregory, and Nurse Wanda Samuel, alongside medical practitioner Dr. Andre Winter. A separate appointment for the Board’s Secretary position will be made by the Governor General at a future date yet to be announced.
The Midwifery Board carries core responsibility for regulating midwifery practice across the nation and upholding rigorous professional standards for the field. Its work is foundational to ensuring that all women and newborns across Antigua and Barbuda have consistent access to safe, high-quality maternity care.
Health Minister the Honourable Michael Joseph publicly welcomed the new appointees, emphasizing the strategic value of the board’s multidisciplinary composition. He noted that combining the expertise of a practicing medical doctor with that of veteran nursing professionals brings unique, complementary strengths to the board’s oversight work.
“Midwifery is an irreplaceable cornerstone of effective maternal and newborn healthcare, and this board bears a critical mandate to uphold professional standards and safe, evidence-based practice,” Minister Joseph stated during the announcement. “By pairing clinical medical perspective with on-the-ground nursing experience, we gain a balanced set of insights that will serve the board well. This collaborative, cross-disciplinary approach will strengthen coordination across healthcare teams, support more informed policy and regulatory decisions, and drive ongoing improvements in care for mothers and infants across Antigua and Barbuda.”
The Ministry of Health has confirmed it is preparing to collaborate closely with the new board members as they begin their official duties. The board’s core priorities will include advancing professional accountability for midwives, supporting continued growth and modernization of midwifery practice, and expanding access to consistent, high-quality maternal and newborn healthcare services for communities across both islands of the nation.
-

Ministry of Health Welcomes Newly Appointed Central Board of Health Members Following Swearing-In CeremonY
On Wednesday, 14 October 2026, a formal swearing-in ceremony for the newly appointed members of Antigua and Barbuda’s Central Board of Health (CBH) took place at Government House. His Excellency Sir Rodney Williams, the nation’s Governor General, officiated the event, inaugurating the team that will serve a two-year mandate leading the country’s public health governance.
Leading the new board is Dr. Teri-Ann Joseph, who takes on the role of chairperson, while Devon Jarvis has been appointed to serve as deputy chairman. The full cohort of board members includes Olivette Wynter, Dion Shaw, Ulla Solomon, J’noure Smith-Kellman, and Eloise Richardson. Loretta Pilgrim will pull double duty, serving both as a board member and the body’s official secretary. One appointee, Cathia Semper, was unable to attend the Wednesday ceremony and will be sworn in at a future scheduled date.
Across the entire team, the new board brings a diverse and robust set of professional backgrounds spanning critical sectors: public health practice, organizational leadership, private sector business, strategic public relations, and grassroots community service. This breadth of experience is positioned to support the board’s wide-ranging mandate across the country’s public health system.
In remarks following the ceremony, Honourable Michael Joseph, Minister of Health, Wellness, the Environment and Civil Service Affairs, extended formal congratulations to the incoming board members, and outlined the outsized importance of the body’s work for the nation. “The Central Board of Health plays an indispensable role in safeguarding the wellbeing of all people across Antigua and Barbuda,” Joseph noted. The board’s core responsibilities span a wide scope of public health priorities: regulating and advancing environmental health initiatives, leading cross-sector disease prevention efforts, identifying and mitigating emerging and existing public health risks, and coordinating nationwide action to both protect and improve population health outcomes.
“I congratulate the newly appointed members and look forward to their contribution in strengthening the work of the Board and addressing existing and emerging public health challenges,” Joseph added. “I am confident that their collective experience and expertise will serve the Board and the people of Antigua and Barbuda well.”
The Ministry also took the opportunity to publicly recognize the contributions of the outgoing CBH, which was led by chairperson Winston Williams. Ministry officials expressed sincere gratitude for the outgoing board’s years of service and commitment to advancing public health across Antigua and Barbuda, and noted that the institution is eager to begin collaborating with the new board to advance ongoing improvements to the nation’s public health services and outcomes.
-

Guyana moves to Restrict Vape Imports Amid Growing Concerns Over Youth Use
GEORGETOWN, Guyana – Facing mounting public alarm over the surging prevalence of vaping among school-aged children and young adults, the Government of Guyana has announced sweeping new restrictions on the import of all vaping products. President Irfaan Ali made the announcement Saturday evening, October 17, confirming that Senior Finance Minister Ashni Singh will issue an official order under the Customs Act, Chapter 82:01, to enforce the import limits.
Under the new policy, all categories of vaping products will face import restrictions, with narrow exceptions granted only after formal approval from the national health minister, the National Tobacco Control Council, or the Tobacco Control Board. President Ali explained that the policy shift comes in response to widespread public outcry over unregulated importation, open market sales, and easy access to vape pens by underage users across the country.
“The restrictions we have authorized align with global public health efforts and reflect what we have heard from parents, teachers, community leaders, young people, and the broader public,” Ali stated.
The president emphasized that the measure is crafted to balance public health protection with access to legitimate medical and therapeutic uses of vaping products, which will remain permitted under close supervision from relevant health authorities. Ali noted that as vaping emerges as a growing public health concern both domestically and across the globe, the Guyanese government has a core responsibility to safeguard public health, especially the wellbeing of youth populations.
Leading global health authorities back the government’s action. The United States Centers for Disease Control and Prevention (CDC) warns that vaping products, commonly referred to as e-cigarettes, are not safe for children, pregnant people, or adults. E-cigarette aerosol can contain nicotine, toxic heavy metals, volatile organic compounds, and other harmful substances that pose long-term health risks.
The vaping crisis is not unique to Guyana; it is a growing public health challenge across the wider Caribbean, where authorities are already grappling with high rates of non-communicable diseases. President Ali pointed out that while vaping products are often marketed as safer alternatives to traditional cigarettes, they are far from harmless, echoing warnings issued by the World Health Organization about the specific risks vaping poses to children and young people.
“Vaping is a challenge that every society around the world currently confronts,” Ali said. “Protecting children, pregnant people, and older adults must remain our top priority. We cannot turn a blind eye to the potential impacts of youth vaping on our young people and our education system.”
Ali concluded by noting that concerns over youth access to vaping products are shared by regional leaders across the Caribbean, who are also collaborating to develop coordinated strategies to address this growing public health threat.
-

Guyana bans recreational vaping products
In a public address delivered via social media webcast on Saturday, 17 October 2026, Guyanese President Irfaan Ali announced imminent government restrictions on the import of all vaping products that have not received formal approval from national regulatory bodies. The policy shift comes amid rising alarms from both domestic communities and global health bodies over the well-documented harms of unregulated vaping on respiratory and mental health, particularly among children and adolescent populations.
Ali emphasized that the new regulatory framework is a direct response to widespread calls for action from parents, teachers, community leaders, young people and broader Guyanese civil society, who have pushed for intervention to curb the unmonitored importation, open sale and rampant use of vaping products across the country. Only vaping products intended for therapeutic and medicinal use will be permitted entry into Guyana, and even these will require formal sign-off from one of three authorized bodies: the Minister of Health, the National Tobacco Control Council, or the Tobacco Control Board.
The President noted that Guyana’s policy aligns with a growing global trend, as dozens of nations around the world have already implemented strict limits on the import and distribution of vaping products to protect public health. He echoed repeated warnings issued by the World Health Organization (WHO), which has long flagged the serious risks of vaping, despite common industry marketing that frames these products as a safer alternative to traditional combustible cigarettes.
“Vaping products can expose users to toxic substances that pose severe risks to human health,” Ali stated during the address. “Vaping is an issue confronting every society, and no one can claim ignorance of the damage it causes to children, school systems, and young people across Guyana, the Caribbean, and the entire world.”
Ali drew particular attention to the unique threat unregulated vaping poses to adolescent development. Early exposure to vaping leads to nicotine addiction that can disrupt healthy brain development in children and teens, he explained, adding that the harms extend beyond individual physical and mental health to shape broader social outcomes for communities. Long-term consequences of early vaping exposure extend beyond individual health, altering social dynamics and leaving lasting negative impacts on young people who encounter these products at vulnerable stages of growth.
Closing the address, Ali called for collective commitment to upholding public health and the social values that will support healthy development for future generations of Guyanese. “I pray that we continue to be guided by faith and strengthen our approach to national development, social protection and the values we want to pass on to the generations of Guyanese,” he said.
-

Een nieuw gebouw is nog geen betere zorg
Even a beautifully renovated hospital ward fitted with cutting-edge new medical equipment cannot guarantee meaningful improvements to care, if patients still face hours-long waits, are forced to repeat their medical history repeatedly due to broken information sharing, receive delayed test results, and leave discharge unclear on their medication regimens. That is the core question raised in a new opinion piece by policy expert Rick Kromodihardjo, as Suriname’s government undertakes a major, multi-million dollar push to repair and upgrade the country’s struggling healthcare system.
Right now, the government is directing substantial investment toward healthcare recovery, with 635 million Surinamese dollars allocated to the Academic Hospital Paramaribo (AZP) to upgrade key departments including the intensive care unit, operating rooms, emergency department, and cardiac care unit. Beyond infrastructure upgrades, the government is also working on strategies to retain skilled healthcare workers, and has launched a new 2026–2030 partnership with the Pan American Health Organization/World Health Organization (PAHO/WHO) focused explicitly on delivering measurable health outcomes.
Kromodihardjo acknowledges that these investments are critical and deserving of recognition: without sustained capital injection, it is impossible to repair the country’s aging healthcare infrastructure or keep core care services operational. But investments alone are not enough, he argues. Once capital projects are complete, a far more important task remains: fixing the broken links in the entire care delivery chain to ensure every stage of a patient’s journey works as intended.
“A building does not treat patients,” Kromodihardjo emphasizes, echoing a recent call by Frank Bueno de Mesquita to reframe healthcare policy around quality of care, health outcomes, and patient experience rather than just physical upgrades. To ground this conversation, Kromodihardjo opens with a fundamental question: what does “good care” actually mean for the people who use it?
A high-end diagnostic scanner, for example, only delivers value to patients if it is consistently operational, staffed by trained personnel, has a steady supply of required parts and materials, allows patients to access scans in a timely manner, sends results directly to the treating clinician, and leads to a clear next step in care. Investments in new equipment and buildings are not the end goal of healthcare reform—they are a starting point. The patient, and their experience of care, should always be the final measure of success.
For the general public, healthcare quality only becomes real when it is felt in daily interactions. Patients judge care by tangible, personal factors: Could I get an appointment when I needed it? Was my prescribed medication in stock? Did my next care provider already know why I was referred? Did I get my test results on time? Did clinicians listen to my concerns? Did I understand what my doctor told me? Did I know what steps to take after I went home?
These are not minor, secondary details. They are the foundation of how patients experience the entire care continuum. The clinical skill of doctors and nurses is unquestionably essential, but even the most advanced medical knowledge falls short if patients do not understand their care instructions, test results are never acted on, or critical patient information is lost when moving between care providers. Good communication is not a “nice extra”—it is a core component of high-quality care.
Kromodihardjo draws a key distinction between patient satisfaction and patient experience, arguing the latter is a far more useful measure of quality. A patient may leave satisfied because their clinician was friendly, even if their treatment was medically substandard. Conversely, a patient may be unhappy about a long wait time, even if they received clinically excellent care. To get an accurate picture of healthcare quality, policymakers need to measure both clinical outcomes and what patients actually experience throughout their care journey—and this gap represents a major untapped opportunity to improve policy.
To address this gap, Kromodihardjo proposes a simple, actionable solution: a National Healthcare Quality Monitor, rather than a costly new large bureaucratic agency. The initiative would start small: select a limited set of key indicators, conduct an initial baseline assessment, then track the same metrics year over year to measure progress. Key indicators could include wait times, availability of essential medications, unplanned downtime for critical equipment, timeliness of diagnostic results, preventable hospital readmissions, successful handoff of patient information between providers, clear communication, and overall patient experience.
The goal of this monitor is not to publicly shame hospitals or individual care providers. Instead, it is designed to identify exactly where improvements are needed, and to measure whether policy interventions actually deliver real results. After a year of reform, this would allow policymakers to report not just how much money was invested, but what tangible, verifiable improvements have actually been achieved for patients.
Crucially, Kromodihardjo notes that many improvements to the care chain do not require billions in new funding. Simple, low-cost changes—clear referral protocols, a system that ensures lab results reach clinicians the same day they are processed, specialists sending timely follow-up reports to general practitioners, nurses checking that patients understand their medication instructions, clear assignment of responsibility for post-discharge care—can deliver major gains. More often than missing funding, these gaps exist because no clear agreements or processes have been put in place.
Healthcare reform requires collaboration across every stakeholder: the government invests and sets policy, insurers purchase and pay for care, hospital leadership organizes internal processes, clinicians deliver skilled care and clear communication, and supporting services like laboratories and pharmacies deliver reliable, timely support. No single stakeholder can claim their work is done and walk away, because patients do not experience healthcare as a collection of separate institutions—they experience it as a single, continuous care journey. A single weak link can undo the good work of every other part of the system.
The current wave of infrastructure investments creates a rare window of opportunity. Kromodihardjo argues that Suriname should seize this moment to not only repair buildings and buy new equipment, but to redesign how care is organized from the patient’s perspective. This would deliver tangible progress the public can actually feel: shorter waits, less time spent searching for medications and supplies, faster test results, smoother information sharing between providers, and clearer guidance for patients about their own care.
That is the kind of progress that matters to patients. Better care sometimes requires more funding, but more often it requires better organization of the resources the system already has. Patients do not come to hospitals for new buildings, fancy equipment, or big budgets—they come for a care chain that actually works.