
Fresh on the heels of the landmark Global Eye Health Summit co-hosted by Antigua and Barbuda, Bangladesh, Guyana, Ireland, Nigeria and the International Agency for the Prevention of Blindness (IAPB), Antigua and Barbuda’s Minister of Health, Wellness, Environment and Civil Service Affairs Michael Joseph convened a dedicated closed-door discussion with three standout young pioneers in the global vision care space. The session was structured to center the firsthand perspectives of the emerging leaders, giving Minister Joseph unfiltered insight into their personal career trajectories, on-the-ground professional challenges, and ongoing community-focused initiatives designed to dismantle barriers to affordable, accessible eye care across their home nations. The three visiting trailblazers bring diverse, lived experience to the global eye health movement: Cynthia Gape, a Botswana-based Software Trainer and Design Lead at Peek Vision, was driven to the field after witnessing her mother navigate preventable vision loss with no nearby access to specialized care, and now builds user-centric digital tools to expand screening reach in remote underserved communities. Samit Sakib Gore, Director of Operations and Innovation at India’s Vision Friend Sakib Gore, leverages nearly a decade of grassroots community outreach experience to build self-sustaining, low-cost eye care models that do not rely on inconsistent external donor funding. Rounding out the group is Juania Mela Mora Cuna Auguste, a Haitian Ophthalmology Nurse Practitioner and co-founder of the Haitian Foundation for the Fight Against Glaucoma (FONHAG), who leads national advocacy campaigns for early, free glaucoma screenings and provides ongoing wraparound support for people living with permanent visual impairment across Haiti. To mark their official visit to Antigua and Barbuda and recognize their exceptional contributions to global public health, Minister Joseph gifted each attendee a signed copy of *A Little Bit of Paradise*, a curated coffee table publication that highlights Antigua and Barbuda’s pristine natural landscapes, vibrant local heritage, and community cultural traditions. The high-level engagement underscored a growing global consensus that centering young, community-rooted leaders is a critical, underutilized strategy to accelerate progress toward universal eye health coverage and eliminate preventable blindness by 2030.
分类: health
-

Cuban Medical Brigade Ends After Thirty-Six Years
On November 3, 2026, Belize’s Ministry of Health and Wellness formally announced the discontinuation of the Cuban Medical Brigade, a landmark cross-border healthcare partnership that has supported the Central American nation’s public health infrastructure for 36 consecutive years. For decades, Cuban medical personnel have served as a core pillar of Belize’s frontline care system, filling chronic staffing shortages in underresourced rural clinics and urban public hospitals that local recruitment efforts had long failed to resolve. Under the new policy framework, the 92 Cuban medical professionals currently stationed across Belize under the brigade program will be offered direct, individual employment contracts to continue delivering patient care, a transition health officials say is calibrated to avoid disruptions to non-emergency and critical medical services nationwide. Speaking in a live phone interview with local outlet News Five, Health and Wellness Minister Kevin Bernard confirmed the cabinet had formally signed off on the decision to wind down the formal brigade program following months of interagency deliberation. “We have been reviewing all feasible pathways to restructure this longstanding partnership for some time, and the cabinet has formally agreed to end the formal brigade operating model,” Bernard explained. “Our top priority is safeguarding uninterrupted care for Belizean communities, so we chose to pursue direct contractual agreements with each of the Cuban health workers currently serving in our country, rather than letting their postings end abruptly. We are now in the process of coordinating one-on-one engagements through the health ministry to finalize these contracts.” When pressed by reporter Britney Gordon on whether all 92 brigade members had already committed to remaining in their posts, Bernard noted that each medical professional retains full autonomy over their employment decision, but expressed cautious optimism that the vast majority would choose to extend their service to Belize. Beyond the transition for existing Cuban medical staff, Bernard outlined parallel long-term investments to strengthen Belize’s domestic healthcare workforce, including targeted scholarship programs for local medical trainees and a $30 million dedicated workforce development initiative aimed at reducing long-term reliance on international medical staffing. When asked to address unconfirmed public speculation that the decision to terminate the formal brigade program was tied to recent diplomatic frictions between Belize and Cuba, Bernard declined to elaborate, noting that all diplomatic matters related to bilateral partnerships fall under the exclusive jurisdiction of Belize’s Ministry of Foreign Affairs.
-
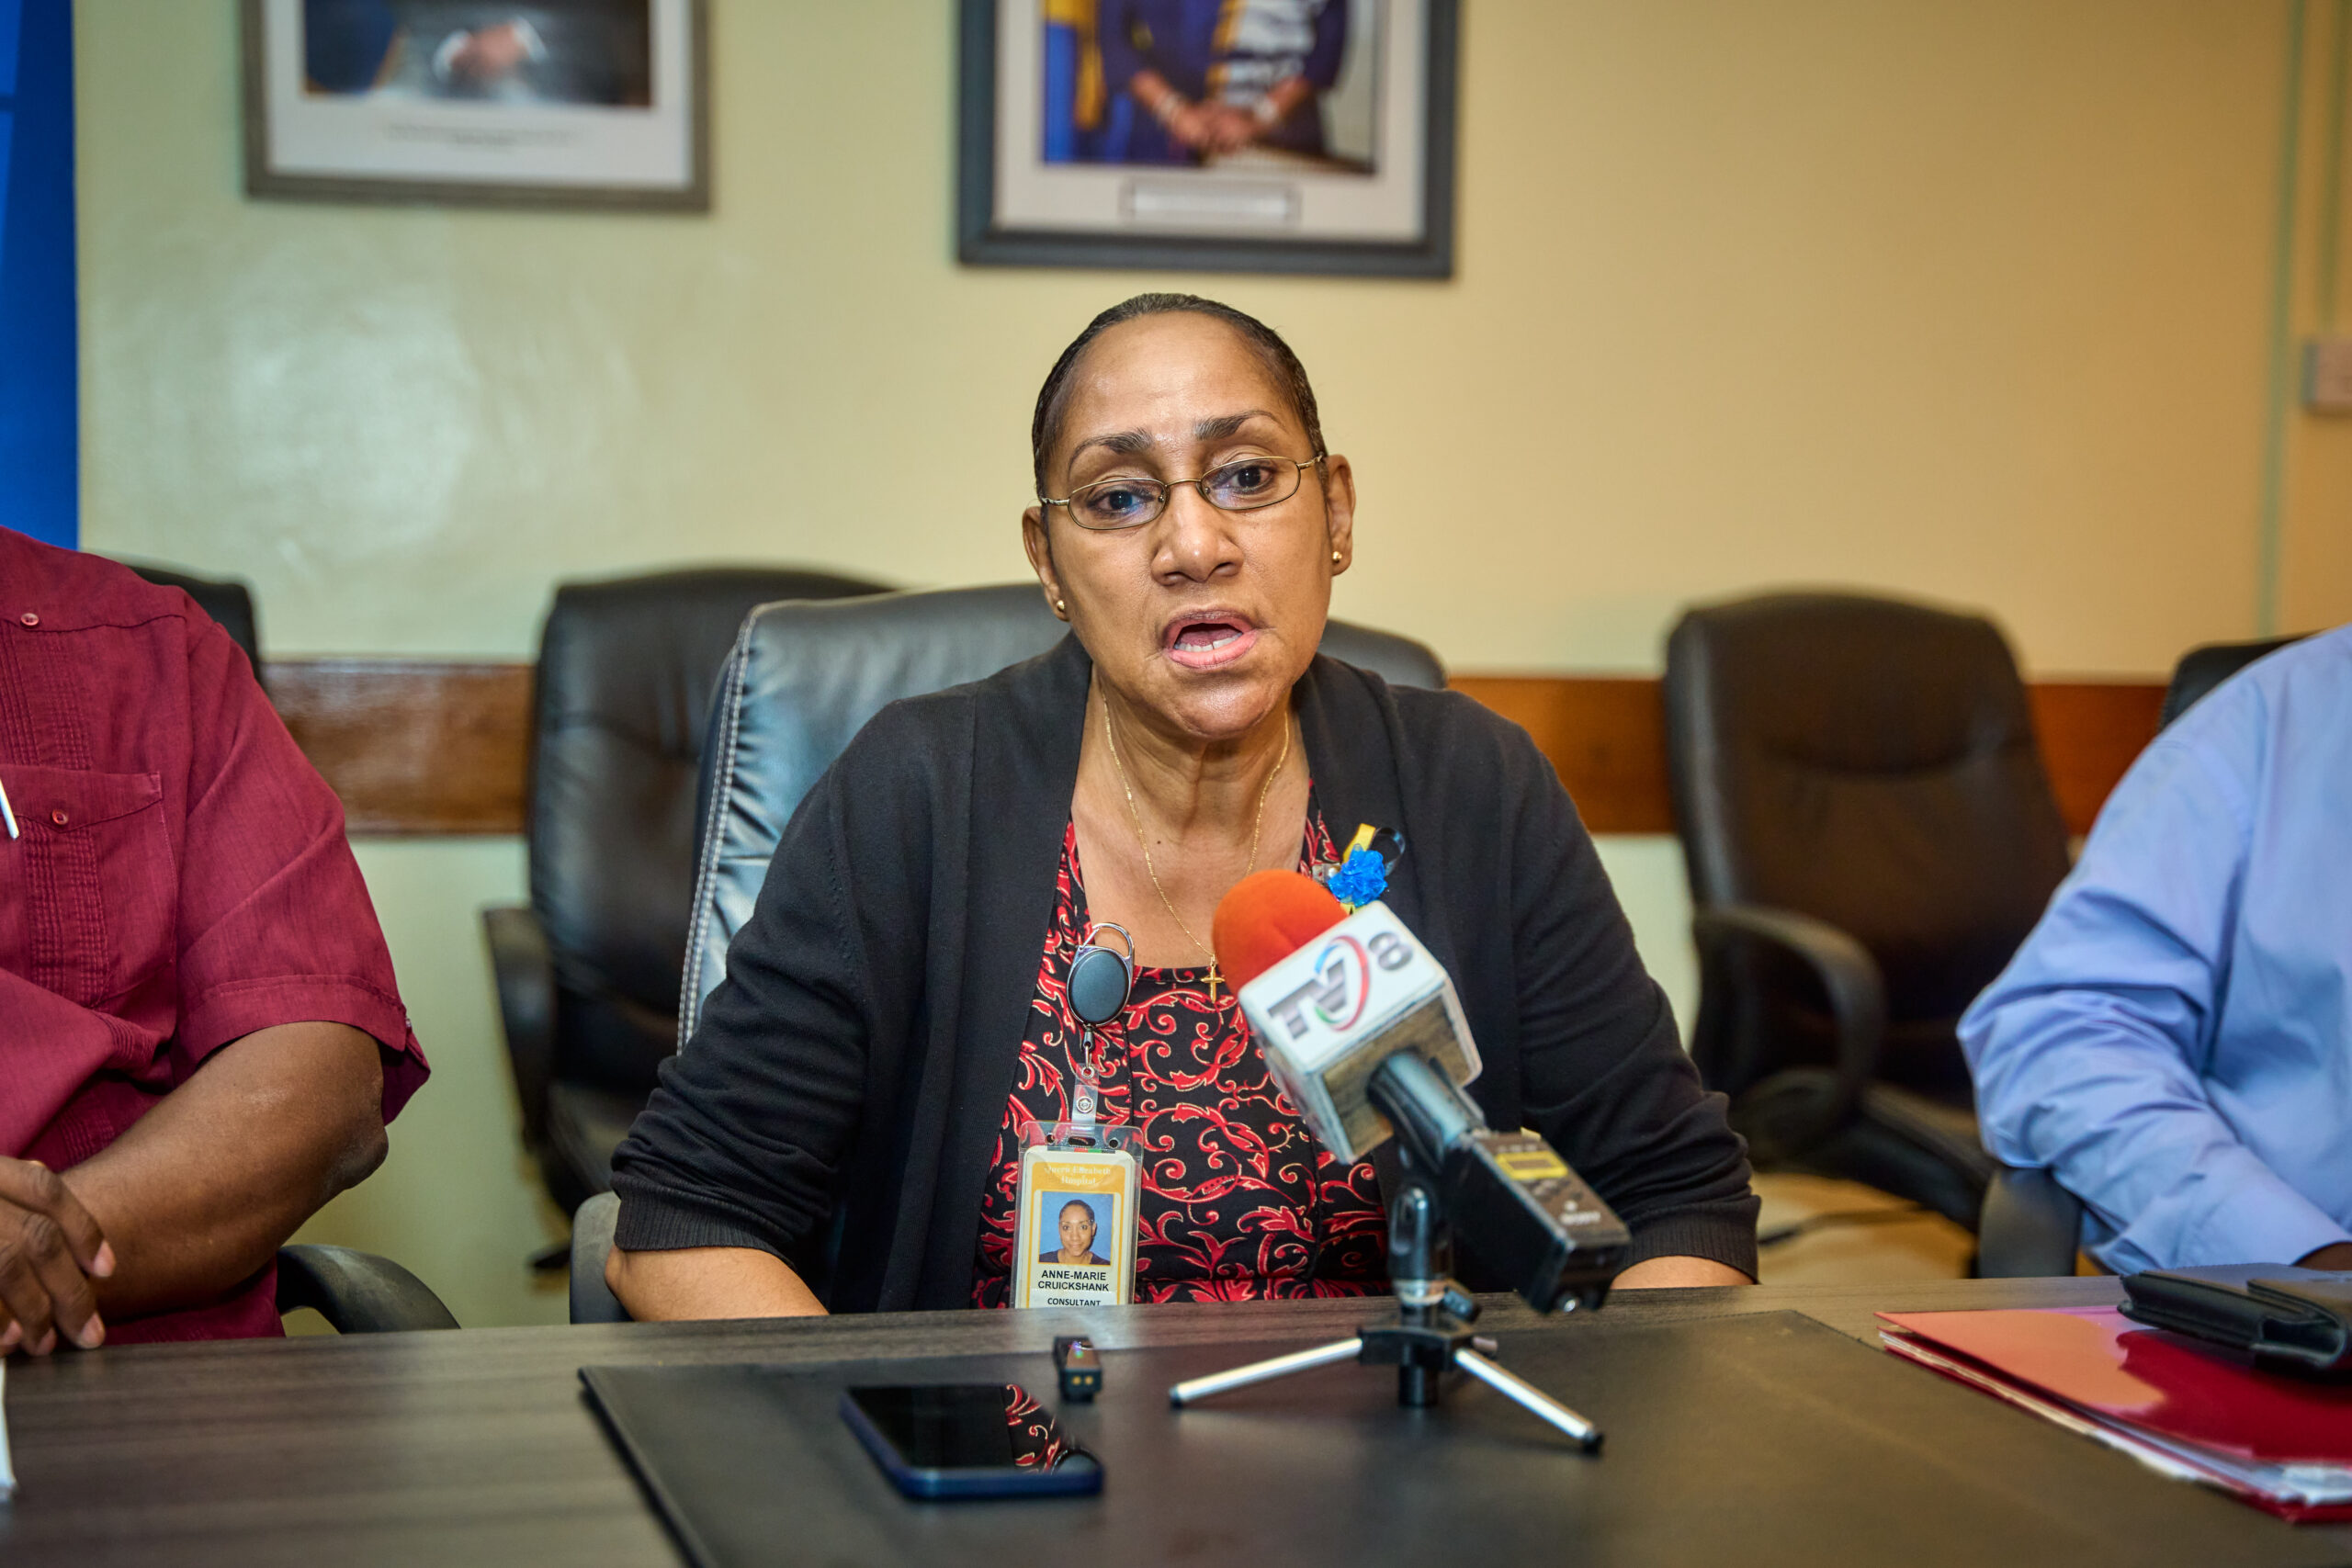
QEH bed shortages leave patients waiting, limit planned surgery
Top health officials at the Queen Elizabeth Hospital (QEH) have publicly outlined a cascading operational crisis that has left emergency patients stuck waiting for inpatient admission and forced widespread pauses on planned elective procedures, as its Accident and Emergency (A&E) department grapples with unprecedented spikes in patient volumes across multiple high-need categories.
A confluence of overlapping stressors is driving the system to its breaking point: surging complications from unmanaged chronic illnesses, a sharp rise in violent and road-related trauma cases, widespread seasonal respiratory infections, and a growing backlog of elderly patients who cannot be safely discharged due to lack of available community or family support. These pre-existing pressures have been drastically amplified by the unexpected loss of dozens of ward beds, triggered by structural fire damage to two units and mould contamination in a third, creating a bottleneck that traps patients in the A&E corridor long after they no longer require acute emergency care.
Addressing reporters during an official press conference held Tuesday to lay out the facility’s urgent challenges, Dr Anne-Marie Cruickshank, consultant and head of the A&E department, detailed that the unit is recording steady year-over-year growth in patients presenting with life-threatening complications from poorly managed non-communicable diseases, including acute myocardial infarctions, strokes, congestive heart failure, and severe trauma wounds. She noted that a large share of these patients have skipped scheduled primary care check-ups, failed to adhere to prescribed medication regimens, and ignored evidence-based dietary guidance for managing their chronic conditions, leading to avoidable emergency admissions that consume disproportionate amounts of clinical staff time, medical supplies, and critical equipment. “Caring for these preventable acute cases drains resources that could otherwise go to other patients who need emergency care,” Dr Cruickshank emphasized.
Trauma caseloads are placing an additional severe strain on overstretched A&E teams, with marked increases in injuries from motor vehicle collisions, gunshot wounds, and stabbings. Dr Cruickshank revealed that the department responded to an external mass casualty incident just last Sunday, triggered by two separate simultaneous road crashes that brought seven severely injured patients through the doors at once. The mass casualty response pulled nearly all on-duty clinical staff to the emergency resuscitation bays, drastically extending wait times for every other patient seeking urgent care that day. In response, Dr Cruickshank issued a public call for all motorists to drive with extreme caution, avoid operating vehicles under the influence of alcohol or drugs, and for community members to manage interpersonal conflicts and frustrations without resorting to violent behaviour.
One of the most underrecognized drivers of the bed crisis, Dr Cruickshank explained, is that 65% of all current A&E patients are aged 65 or older. While many of these older adults can be safely discharged home or to community care after their acute symptoms are stabilized, hospital staff are increasingly encountering situations where family members refuse to take their elderly relatives back home, effectively abandoning them to remain in the hospital long after they no longer need acute medical care. “Our A&E is designed exclusively for short-term acute emergency treatment, it has none of the dedicated staffing or facilities to support long-term residential care for older patients, and this unplanned long-term occupancy is eating up beds that should go to newly arriving emergency cases,” she noted. The department is also seeing sharp spikes in severe influenza and other respiratory infections, disproportionately affecting elderly people and infants, who face far higher risks of complications that require inpatient admission. Dr Cruickshank urged all members of the public, especially caregivers for young children and older adults, to re-adopt the low-cost public health precautions widely used during the COVID-19 pandemic, including consistent mask-wearing in crowded indoor spaces, rigorous handwashing, and regular use of hand sanitizer to cut down community transmission of respiratory viruses.
Dr Carlos Chase, the hospital’s Director of Medical Services, provided additional granular data on the scale of the crisis, confirming that 40 patients at QEH are currently relying on mechanical ventilator support, while a further 55 patients are fully stable and no longer require acute hospital care but remain admitted with no available discharge placement to move to. The entire system’s capacity has been gutted by the temporary closure of three inpatient wards: Wards C7 and C8 were damaged in an earlier fire, while Ward B4 was taken offline after unsafe mould growth was discovered. The loss of these ward beds has completely broken the normal patient flow from A&E to inpatient wards, creating the massive admission backlog and forcing the hospital to postpone almost all non-urgent elective surgeries, which require guaranteed post-procedure inpatient beds for 24 to 48 hours of monitoring.
However, Dr Chase outlined a clear path to restoring normal operations, noting that full remediation work on the fire-damaged and mould-affected wards is already well underway. All repairs and safety testing for Wards C7 and C8 are on track to be completed within 30 days, and the hospital is on track to partially or fully reopen all three affected wards in as little as one to two weeks, pending final safety inspections and staffing capacity assessments. As soon as the additional beds come back online, the hospital will immediately begin clearing the backlog of postponed elective procedures, with the goal of returning to full pre-crisis surgical volumes as quickly as possible. “We are optimistic that within the next 14 days, we will have most or all of these wards back in service, and we can resume delivering the full range of planned elective surgeries for our community, as long as our remediation work meets all required safety standards,” Dr Chase confirmed.
-

Rise in flu adds pressure on QEH
During a Tuesday press conference hosted at Queen Elizabeth Hospital (QEH) in Barbados, top health authorities laid out the multifaceted pressures currently stretching the national healthcare system thin, while rolling out targeted public guidance to ease the burden and reduce severe health outcomes. Chief Medical Officer Dr Kenneth George clarified that the recent uptick in respiratory illnesses, including confirmed detections of influenza A, influenza B, rhinovirus, and a small number of COVID-19 cases, aligns with standard seasonal patterns that mirror flu surges in other global regions. Crucially, Dr George emphasized that this respiratory spike is far from the sole driver of QEH’s overstretched capacity: a confluence of overlapping pressures has converged to push patient volumes to elevated levels. These contributing factors include a rising prevalence of unmanaged non-communicable chronic conditions, the country’s rapidly ageing population that often requires extended inpatient stays, and a steady stream of severe trauma and road traffic accident cases that demand specialized hospital care. “We have navigated similar scenarios in the past, but this period has seen multiple distinct stressors align all at once,” Dr George noted. To mitigate the strain on tertiary care facilities, the Chief Medical Officer issued two key public calls to action. First, he urged all Barbadians experiencing early symptoms of illness to prioritize visiting their primary care provider — whether a private family physician or a public community polyclinic — rather than waiting until conditions escalate to emergency severity, noting that early clinical intervention drastically improves patient outcomes while reducing unnecessary admissions to QEH. Second, he appealed to residents living with non-communicable diseases to take proactive ownership of their health management, through consistent exercise, balanced dietary choices, and gradual healthy weight maintenance, small daily adjustments that can prevent complications that would otherwise require long-term hospital stays. Joining the briefing, Dr Corey Forde, QEH’s Director of Clinical and Diagnostic Services and a leading infectious disease specialist, confirmed that the emergency department’s rising influenza caseload matches concurrent trends observed across the Caribbean and around the world, noting that neighboring St Vincent and the Grenadines had recently held a parallel public health briefing to address the same seasonal pattern. Dr Forde added that QEH has managed elevated respiratory illness volumes for the past four to six months, with the most recent shift being a sharp, broad rise in patients seeking emergency care for acute symptoms. He specifically highlighted the heightened risk facing vulnerable demographic groups: young children and elderly residents, including those residing in private homes, long-term care facilities, or already receiving inpatient treatment, are far more likely to require hospital admission for respiratory complications than otherwise healthy younger adults. Dr Forde urged all residents who develop respiratory symptoms to take extra precautions around at-risk household and family members, including avoiding close contact with elderly relatives if they have recently attended large social gatherings and developed subsequent mild illness, to prevent avoidable severe cases that would further burden the hospital system.
-

PARADISE INTERRUPTED | What’s really killing us?
During a recent community workshop hosted by Caribbean agricultural non-profit Helen’s Daughters, University of the West Indies senior lecturer and program director Dr. Kadamawe Knife shared a provocative observation that has lingered with event attendee and Helen’s Daughters founder Keithlin Caroo-Afrifa: substandard, heavily imported food supplies are contributing to more preventable deaths across the Caribbean than gun-related violence. The comment lands with particular weight in Saint Lucia, where widespread public outcry and targeted policy action have long centered on the visible, traumatic toll of gun violence, which dominates local headlines, ravages marginalized communities, and leaves countless families reeling in public, shared grief. Yet Dr. Knife’s remark forces a difficult, long-overdue reckoning with a far quieter, normalized wave of loss: the thousands of annual deaths that unfold unremarkably in hospital wards and private homes, written off as inevitable outcomes of age or pre-existing illness, even as they claim working-age people in their prime. The Saint Lucian Ministry of Health’s official public health data confirms that noncommunicable diseases (NCDs) – including cardiovascular conditions, stroke, type 2 diabetes, and multiple forms of cancer – make up more than 80% of all recorded fatalities across the island. For context, the Organization of American States documented 73 homicide deaths in Saint Lucia in 2024, a staggering, unacceptable toll of human life that no one seeks to minimize. Every lost life, whether to gun violence or chronic diet-related illness, carries equal weight, and every grieving family deserves full public support and recognition. This framing is not an attempt to rank one tragedy as more urgent than the other, but to interrogate a stark double standard in public policy: why do highly visible, violent threats trigger immediate, coordinated government responses, while slow-moving, diet-linked public health crises are dismissed as unavoidable personal misfortune? The data does not claim that poor diet alone causes every NCD death, just as not all homicides involve firearms: tobacco use, excessive alcohol consumption, sedentary lifestyles, and genetic predispositions all play documented roles in chronic disease development. Even so, decades of peer-reviewed public health research confirm that unbalanced, nutrient-poor diets are a leading modifiable risk factor for preventable NCD mortality. All too often, casual local discourse frames small amounts of added sugar or mild high blood pressure as trivial, harmless inconveniences, ignoring the cascading societal costs: lost workplace productivity, overstretched family caregivers, and entire households forced to restructure their lives around long-term chronic illness management. Familiarity with these outcomes should never be misread as an unavoidable, unchangeable reality. Equally harmful is the pervasive myth that healthy eating is purely a matter of personal willpower and individual discipline. A 2023 United Nations food security report found that 52% of all Caribbean residents could not afford a nutritionally adequate, balanced diet as far back as 2020, meaning more than half the regional population is effectively locked out of accessible healthy eating options regardless of their personal choices. Telling a low-income Saint Lucian household to prioritize fresh leafy greens and local root vegetables is meaningless when those same households must choose between buying produce and covering their monthly electricity bills. Not all imported food is inherently unhealthy, nor is every locally grown crop automatically nutrient-dense: affordability, geographic access, and daily convenience are the primary forces that shape what ends up on the average family’s dinner plate. These barriers are not accidental, but the legacy of centuries of colonial agricultural policy that structured Caribbean food systems entirely around export crops for overseas markets, at the direct expense of developing robust local food production for domestic consumption. The region inherited a food economy built for extraction, not community sustenance – and post-independence governments have rarely done enough to dismantle that legacy and build systems designed first and foremost to feed local populations. This is why Caroo-Afrifa argues that the agricultural sector should no longer be valued solely as a profit-driven economic industry, but recognized as a core public health public good. A reimagined local food system would center nutritional outcomes as a key metric of success, not just total crop tonnage, and prioritize integrating local smallholder farmers into reliable, institutional supply chains for schools, public hospitals, and government food assistance programs. This model is already being piloted through Helen’s Daughters’ cross-community programming, which pairs hands-on sustainable farming training for women smallholders with public nutrition education, community cooking demonstrations, and simplified, budget-friendly recipes designed to make local produce accessible and easy to prepare for time-strapped working families. The organization’s work goes far beyond helping women farmers sell their harvests: it closes the gap between a vegetable sitting on a market stall and that vegetable becoming a nourishing meal on a family dinner table. For fresh produce to deliver public health benefits, households must be able to afford it, know how to cook it in appealing, time-efficient ways, and fit meal preparation into already overcrowded daily schedules of work and caregiving. This vision does not demand a full, unrealistic return to the arduous traditional agrarian lifestyles of previous generations; instead, it adapts longstanding Caribbean culinary traditions and local food knowledge to fit the realities of 21st century working life. Tradition and modern convenience do not have to be opposing forces, and the sectors of agriculture, public health, and education do not need to operate in isolated silos. The measure of a successful local food system is not how much it can export for overseas profit, but how effectively it supports the entire population to live long, healthy lives. This approach does not ask small-scale farmers to single-handedly solve the national public health crisis, or replace evidence-based clinical medical care with generic dietary advice. It simply requires centering preventative public health priorities at every stage of the food supply chain, from farm production to retail distribution to public institutional meal services. Public safety cannot be achieved through policing and law enforcement alone. Some of the most transformative, life-saving public investments will be made on small family farms, in public school kitchens, and at neighborhood community markets. A nation cannot call itself truly secure just because its residents are protected from violent harm: it must also guarantee every citizen a fair, equal opportunity to live a long, thriving life free from preventable chronic illness. For a region that proudly markets itself as a tropical paradise, that basic standard of collective wellbeing should not be an unreasonable, unachievable demand.
-

Wie betaalt de hulp voordat iemand breekt?
Published November 3 at 11:18 by Starnieuws, this opinion piece by local healthcare advocate Rick Kromodihardjo draws a direct parallel between physical and mental health care inequities in Suriname: when a patient reports weeks of persistent chest pain, no responsible medical provider would advise them to return only after suffering a full heart attack, yet the current national mental health system effectively operates under that exact flawed framework. The piece outlines that early warning signs of declining mental well-being – including chronic insomnia, rising anxiety, reduced workplace function, social withdrawal, and a pervasive sense of lost control – are often dismissed as non-urgent, even though timely, low-intensity support could prevent progression to full psychosis, involuntary hospitalization, or life-threatening crisis.
The first major barrier blocking access to that early intervention is systemic: people experiencing mild to moderate mental distress have no clear guidance on where to turn for help, who is qualified to support them, and how they will cover associated costs. The author emphasizes that national policy should not prioritize only crisis response, but instead proactively build structured support long before a person’s condition deteriorates to acute severity.
A core focus of the analysis is the link between insurance policy and accessible care, noting that Suriname’s national SZF public health insurance scheme only covers a maximum of 10 psychology consultations per calendar year, capped at SRD 100 per session. Data from the 2024 WHO Mental Health Atlas confirms that more than half of all people in Suriname seeking psychotherapy and other formal psychological treatment pay between 51% and 100% of all costs out of pocket. Earlier this year, Suriname’s Undersecretary of Public Health acknowledged that this limited reimbursement structure creates a prohibitive access barrier, and publicly stated the SZF coverage framework requires urgent revision.
The author argues that the arbitrary 10-visit annual cap is inherently counterproductive, and that care volume should be determined by a patient’s clinical needs and personalized treatment plan, not a rigid calendar-based limit. It is contradictory, he notes, for public health campaigns to urge citizens to seek early mental health support while shifting nearly all the upfront cost burden to patients at the earliest, most preventable stage of care. Drawing on his own professional experience working with the SZF scheme, the author explains that health insurance design does not only cover medical bills: it directly shapes when and where people choose to seek care. When reimbursement levels are negligible, access remains severely constrained. He calls for a full, transparent review of funding across the entire mental health care continuum, spanning early detection, primary care triage, psychological counseling, outpatient psychiatry, crisis response, inpatient hospitalization, and post-discharge aftercare, to confirm the country is not directing nearly all its mental health spending only after a patient’s condition has become severe and unmanageable.
The piece also pushes back against the false narrative that psychologists and psychiatrists are competing providers, noting that the two professions serve distinct, complementary roles in a cohesive care pathway. Not every person living with anxiety, grief, persistent low mood, or chronic stress requires specialized psychiatric care, and not every severe psychiatric condition can be resolved with a small number of talk therapy sessions. The author stresses that psychiatrists cannot be expected to single-handedly resolve gaps created by insufficient earlier support, and psychologists cannot be tasked with solving systemic funding shortfalls that force patients to cover nearly all their own care costs. To properly support both provider groups, policymakers must include frontline psychologists and psychiatrists in the design of referral rules, funding structures, and aftercare programs, as these clinicians witness firsthand the daily harms of the current system: patients who arrive for care far too late, drop out of treatment due to cost, are misdirected through broken referral pathways, or fall entirely out of official care records.
Recent public safety data underscores the urgency of these reforms: the Suriname Police Corps recorded eight confirmed suicide cases in the four-week window between September 1 and September 28. While the author notes this small sample does not confirm a long-term upward trend, every individual case represents a preventable tragedy, and the high volume of deaths in such a short window makes clear that mental health is not a niche concern reserved for dedicated public mental health agency staff, psychiatrists, and psychologists alone. It impacts families, schools, employers, primary care providers, insurance carriers, and every segment of Surinamese society.
In November 2025, the Ministry of Public Health launched a formal multi-stakeholder consultation process to develop the upcoming 2025–2030 National Strategic Plan for Mental Health and Suicide Prevention, with working groups identifying core bottlenecks including pervasive social stigma, chronic underinvestment, critical staffing shortages, and fragmented, disconnected care pathways. The author frames this policy process as a once-in-a-generation opportunity to build a cohesive, continuous national mental health care chain that functions effectively before patients reach crisis point.
To deliver on that vision, the primary care physician must be positioned as a trusted first point of contact for patients, with clear training to conduct basic mental health screenings and issue streamlined referrals. Psychological counseling must be made genuinely affordable through expanded SZF coverage, the referral pathway to specialized psychiatrists must be clearly mapped for patients and providers alike, and the newly launched national 114 crisis support hotline must be maintained with sufficient staffing to support acute, high-risk cases in partnership with the country’s primary public mental health agency. After a patient’s condition is stabilized following a crisis, they must be smoothly transitioned back to appropriate lower-intensity ongoing care to prevent recurrence.
The author notes that these improvements do not require massive new capital construction or billions of dollars in new spending: most of the needed changes rely on clear formal care agreements, standardized referral protocols, structured cross-provider follow-up reporting, and clear public accountability for which stakeholder is responsible for each stage of a patient’s care. The government must implement standardized tracking to identify points where patients fall out of the system, including long wait times, treatment dropouts due to cost, unprocessed referral requests, and cases where patients are only identified once their condition has progressed to severe stages. All funding allocations for each segment of the mental health care continuum must also be made fully transparent to the public.
The piece closes by arguing that the country should no longer wait to take mental health funding seriously until a patient becomes suicidal, experiences a full psychotic break, or is completely unable to function in daily life. A well-designed mental health system does not only fund emergency response to catch people after they have already fallen into crisis: it invests in proactive, early support to catch people before they reach that breaking point. The author rejects the current fire department-style model of care that only springs into action once a patient’s life is already on fire, arguing that the national priority should be to make early mental health support universally accessible before crisis care becomes necessary. While some crises can never be fully prevented, every person who receives timely, appropriate early intervention represents a tangible win for public health. Dedicated crisis response services will always remain essential, but the greatest long-term progress will come when enough people receive support early enough that they never need to access crisis care in the first place.
-

Someone always pays: Health Financing Primer, Part 1
A prominent Grenadian medical expert and Commonwealth Scholar, Dr. Ishma Harford, has laid bare widespread public misperceptions about the island nation’s health funding landscape in a non-partisan educational health column published via NOW Grenada. For years, most Grenadians have assumed the national government is the primary funder of local health services, but 2023 data from the WHO Global Health Expenditure Database upends that long-held assumption entirely. Official 2023 figures show government contributions make up just 45% of Grenada’s total annual health expenditure, while direct out-of-pocket payments from households for pharmacy purchases, lab tests, private doctor consultations and other immediate care costs account for a staggering 48% of all health spending, the highest rate across all Organisation of Eastern Caribbean States (OECS) member nations and far above the regional 30% average. Dr. Harford argues that framing government health spending as a separate, independent pool of resources is a misleading “mirage”, as every dollar the state allocates to health programs originates directly from Grenadian households via income taxes, value-added tax on daily groceries, and import duties on consumer goods. When combined, direct out-of-pocket costs and indirect tax contributions mean local residents fund a full 93% of the country’s total health expenditure, making them far and away the single largest stakeholder in the national health system, rather than passive recipients of state-provided charity. Under this framework, Dr. Harford explains, the government’s proper role is not a benevolent health provider, but a fiduciary proxy entrusted with public tax dollars to deliver services that meet three core WHO-mandated health system benchmarks: improving population health outcomes, responding fairly to public needs, and shielding residents from crippling medical-related financial hardship. By these global standards, he notes, Grenada’s health system is currently failing on two critical fronts. First, while some policymakers claim the 48% out-of-pocket spending rate does not push large numbers of households into medical poverty, this metric ignores the thousands of low-income families who forgo necessary care entirely because they cannot afford upfront costs, a gap that leaves them technically “financially protected” on official paperwork even as their health deteriorates. Second, widespread systemic failures including persistent medication stockouts, multi-month wait times for routine appointments, and lack of transparent accountability for resource mismanagement are often incorrectly framed as limits on government generosity, rather than failures to deliver services that residents have already paid for twice, once via taxes and once at the point of care. Dr. Harford emphasizes that not all wait times are inherently unreasonable: delays allocated based on clinical need, clearly communicated to patients, and bounded by published public service standards represent a system operating responsibly within its resource limits. But unaccountable delays caused by unreported empty medication shelves or unmanaged administrative waste represent a breach of the public’s trust in the proxy they have empowered to manage their health funds. He concludes by urging Grenadian residents to demand full transparency, clear public receipts for all public health spending, and greater accountability for the stewardship of the billions of dollars in combined household and tax funds that flow through the national health system each year. NOW Grenada notes that all opinions expressed in the column belong solely to Dr. Harford, and the platform bears no responsibility for contributor-submitted content.
-

Prime Minister’s Vision Initiative Offers Free Reading Glasses at Jennings South Mall Today
Starting on Tuesday, November 3, 2026, residents across Antigua and Barbuda can receive no-cost reading glasses as the newly launched Prime Minister’s Vision Initiative officially opens its first operational site at Unit 6, Jennings South Mall. The public health outreach program, running through November 6, is a collaborative effort between the Office of the Prime Minister, the Ministry of Health, Wellness, Environment and Civil Service Affairs, and global nonprofit vision care organization RestoringVision to address unmet near-vision needs that often hinder daily tasks, work productivity, and quality of life for local community members. The pop-up vision clinic follows structured operating hours: 10 a.m. to 3 p.m. from Monday through Thursday, and 10 a.m. to 2 p.m. on Fridays. Distribution of the free reading glasses operates on a first-come, first-served basis, and all attendees are required to present a valid government-issued national photo ID to participate. Program organizers have confirmed that additional pop-up clinic locations will be rolled out and announced on a rolling schedule in the coming weeks, as the initiative works to expand equitable access to corrective near-vision support to underserved neighborhoods across the twin-island nation. The program is guided by the core public outreach slogan: “Clear Vision. Better Lives. Stronger Communities.”, framing the effort as a community-focused investment in public well-being that reduces avoidable barriers for residents who may not otherwise afford corrective reading eyewear.
-

Antigua and Barbuda Joins Global Leaders in Advancing Commitments to Eye Health as Global Eye Summit Concludes
Hosted by the Government of Antigua and Barbuda alongside co-host nations Bangladesh, Guyana, Ireland, and Nigeria, in technical partnership with the World Health Organization (WHO) and under the secretariat coordination of the International Agency for the Prevention of Blindness (IAPB), the landmark Global Eye Summit wrapped up its proceedings today at the Sir John E. St. Luce Conference Centre. The high-profile gathering brought together heads of government, multilateral institution representatives, development stakeholders, civil society groups, and private sector leaders to align on actionable strategies to expand equitable access to quality eye care worldwide, and embed eye health priorities within universal health coverage roadmaps. In his official closing address, Antigua and Barbuda’s Minister of Health, Wellness, Environment and Civil Service Affairs Michael Joseph framed the summit’s collective outcomes as a pivotal turning point that moves long-held global eye health ambitions from policy rhetoric to tangible, community-focused impact. Joseph revealed that 57 participating national governments have formally tabled binding domestic commitments, unlocking a combined US$1.23 billion in earmarked public funding for national eye health programming – a shift that signals a widespread global move toward sustainable, country-led financing models that reduce overreliance on external donor aid. Several targeted priority pledges emerged from the summit’s working sessions: 29 nations committed to scaling up child eye health services via nationwide rollouts of school-based vision screening programs, streamlined early detection pathways for vision impairments, and expanded access to low-cost, quality prescription eyewear, with these efforts backed by 8 private sector partners and 53 civil society organizations, plus a formal UNICEF pledge to support 25 countries to deliver vision screening to 90 million children across low and middle-income regions. A further 42 governments agreed to implement targeted policy reforms to cut barriers to affordable glasses, including full alignment with WHO’s SPECS initiative, strengthened regulatory standards for eyewear quality, and the full removal of import tariffs and consumption taxes on prescription glasses to reduce costs for households. Regional collective commitments were also formalized during the event, with the Caribbean Community (CARICOM) and 18 Pacific Island nations announcing coordinated regional action plans tailored to address unique gaps faced by small island developing states and geographically dispersed, resource-strapped health systems that have long struggled to deliver equitable eye care services to remote communities. One of the summit’s most transformative milestones was the official launch of WHO’s SEE 2045 initiative, which establishes the world’s first global target to eliminate avoidable cataract – marking only the second noncommunicable disease in WHO’s 75-year history to receive a formal global elimination roadmap. Antigua and Barbuda was named among the first five pilot nations to join the SEE 2045 effort, alongside Bangladesh, China, Kenya, and Nigeria. The summit’s overarching unifying framework, the St. John’s Global Compact for Eye Health, was formally adopted during the closing plenary, consolidating all government, private sector, and civil society pledges under a unified structure that standardizes action tracking, investment accountability, and transparent progress reporting. At the time of the closing session, 187 cross-sector stakeholders had already formally endorsed the Compact, with organizers confirming the document will remain open for additional signatories from governments and partner organizations in the months following the summit. Minister Joseph extended special recognition to the IAPB for its work as the summit’s secretariat, calling on the global blindness prevention body to continue facilitating cross-stakeholder collaboration to ensure no pledged commitment falls through the cracks. “Every promise has been made, and the St. John’s Compact is now formally adopted,” Joseph stated in his closing call to action. “Our work starts today, not when we return home. Every partner around this table must deliver on the pledges we have made here in St. John’s, to ensure no person is left behind due to preventable or treatable vision loss.”
-

Duchess of Edinburgh Visits Primary Eye Care Unit at Gray’s Green Community Centre
Earlier today, Antigua and Barbuda’s Minister of Health, Wellness, Environment and Civil Service Affairs Michael Joseph extended a formal welcome to Her Royal Highness The Duchess of Edinburgh for a guided tour of the recently soft-launched Primary Eye Care Unit housed at the Gray’s Green Community Centre. The high-profile royal visit was curated to highlight the Antiguan and Barbudan government’s ongoing strategic investments to upgrade national eye care infrastructure, with a specific focus on rolling out community-centered services that make routine vision screening, early condition detection, and timely low-cost treatment accessible to residents who previously faced barriers to specialized vision support. During the tour, The Duchess met face-to-face with leadership from the cross-sector coalition of local and global organizations that have partnered to bring the new unit to fruition, including Cure Blindness, VisionSpring, Trinidad Eye Hospital, Orbis International, and RestoringVision. Distinguished guests in attendance alongside the royal visitor included Kathleen Sherwin, President and Chief Executive Officer of Orbis International, His Excellency Dr. Walton Aubrey Webson, and a cohort of senior leadership staff from the Ministry of Health. Four frontline public health nurses, who recently returned to the country after completing an intensive specialized advanced training program focused on primary eye care delivery in India, were also on site to showcase the unit’s functional capabilities. The nurses led live, interactive vision screening demonstrations to illustrate the full scope of routine services the facility will offer once fully operational. As Minister Joseph noted, the new community-based unit is a core pillar of the health ministry’s multi-year roadmap to eliminate gaps in local access to essential vision care, by moving services out of centralized hospital campuses and directly into residential neighborhoods to cut down on travel time and associated costs for underserved populations. While the facility has completed its soft opening phase to test workflows and train on-site staff, it remains closed to the general public for now, as administrative teams work to finalize delivery of remaining specialized medical equipment and formalize all operational protocols. The government has scheduled the unit’s official public launch and full rollout of services for January 2027. Minister Joseph also laid out the administration’s longer-term 5-year strategic goal to build and commission a standalone, full-service dedicated national eye hospital, a landmark investment that will drastically expand the country’s capacity to deliver complex specialized vision care and reduce the need for patients to travel overseas for advanced treatment. Health ministry leadership emphasized that the success of the ongoing national eye care expansion agenda is directly tied to sustained, collaborative partnerships with international non-profit allies and skilled local healthcare workers, as the collective effort works to drastically reduce rates of preventable blindness across Antigua and Barbuda.