分类: health

  • Dominican Republic launches prenatal care training in Dajabón and Elías Piña

    Dominican Republic launches prenatal care training in Dajabón and Elías Piña

    In the Dominican Republic, national health authorities have rolled out a new frontline training initiative designed to upgrade prenatal care services and lower preventable maternal and newborn health risks across two underserved border provinces, Dajabón and Elías Piña.

    The joint effort, led by the country’s Ministry of Health and National Health Service (SNS), brings together global partners for both financial and technical backing: the Korea International Cooperation Agency (KOICA) is covering the program’s core costs, while the Pan American Health Organization/World Health Organization (PAHO/WHO) provides expert technical guidance. The training forms a core component of a broader long-term project targeted at strengthening primary-level maternal and child health services across the two provinces.

    Dominican Health Minister Víctor Atallah emphasized that expanding access to high-quality prenatal care stands as a top public health priority for the current administration. He noted that consistent, routine prenatal checkups are a critical first line of defense, allowing clinicians to catch potential health risks early, head off life-threatening complications before they escalate, and guarantee that expecting mothers receive timely, evidence-based care throughout their pregnancy.

    The intensive three-day training curriculum covers a full spectrum of essential prenatal care skills, including comprehensive whole-pregnancy health assessments, detailed medical history documentation, evidence-based prenatal nutrition guidance, maternal vaccination protocols, patient counseling for expecting families, continuous fetal monitoring techniques, and personalized birth planning. Trainees also build specialized capacity to recognize and respond to urgent obstetric warning signs, such as pregnancy-induced hypertension, abnormal bleeding, and maternal infections. Additionally, the program strengthens participants’ ability to coordinate community-level health monitoring and streamline referrals for high-risk pregnancies that require advanced hospital care.

    SNS Director Julio Landrón explained that the overarching goal of the training program is to advance health equity, ensuring every pregnant woman in the two provinces can access timely, comprehensive prenatal care no matter her residential location or socioeconomic status. As part of the broader project, health authorities will also upgrade infrastructure and services at 31 existing prenatal care centers in Dajabón and 19 more in Elías Piña, with coordinated outreach involving provincial hospitals, practicing physicians, nursing staff, community health promoters, and local basic health management teams.

  • Ministry of Health Recalls Three Medications Over Quality and Contamination Concerns

    Ministry of Health Recalls Three Medications Over Quality and Contamination Concerns

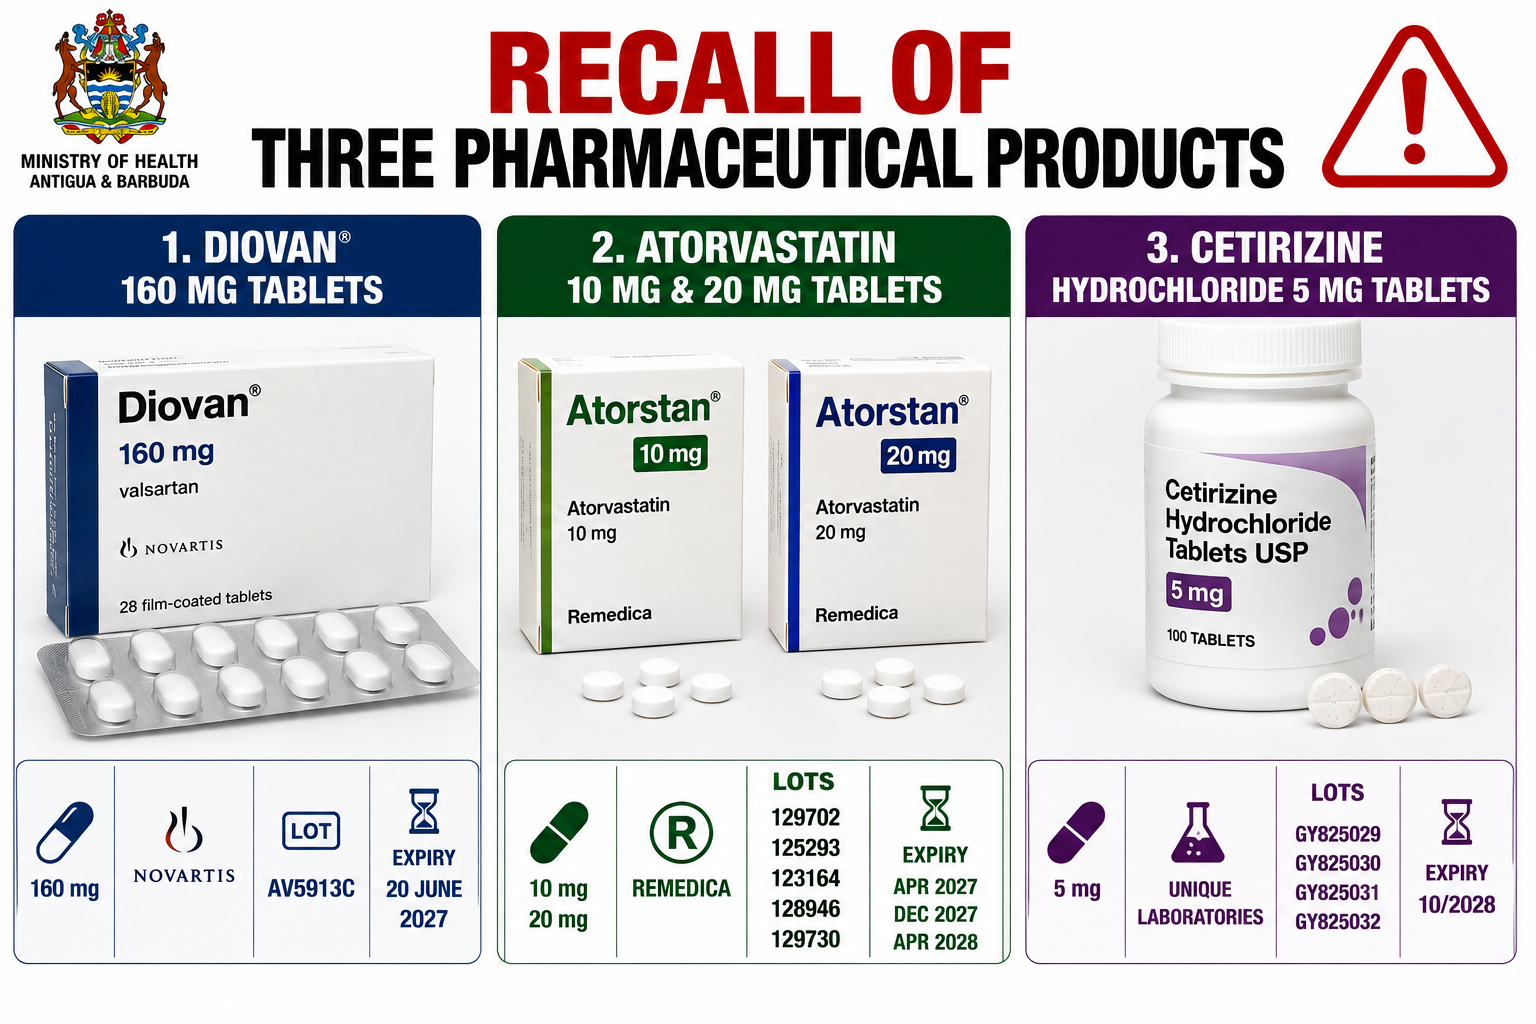
    The pharmaceutical regulatory arm of Antigua and Barbuda’s Ministry of Health, Wellness, the Environment and Civil Service Affairs has issued an official alert to the public, medical providers, pharmacies, and supply chain stakeholders, announcing the voluntary and precautionary recall of three categories of widely used medications distributed across the island nation. The three affected product lines include specific batches of Novartis’ Diovan 160 mg tablets, Remedica’s Atorstan atorvastatin 10 mg and 20 mg tablets, and Unique Pharmaceutical Laboratories’ Cetirizine Hydrochloride 5 mg tablets.

    The first recall, formally announced by the U.S. Food and Drug Administration on August 4, 2026, is a voluntary withdrawal initiated by global pharmaceutical manufacturer Novartis for one specific lot of Diovan 160 mg tablets, a leading valsartan-based medication. Diovan, an angiotensin II receptor blocker, is commonly prescribed to manage high blood pressure and treat chronic heart failure. The recall was triggered after quality testing revealed the product failed to meet mandatory dissolution specifications – a quality standard that measures how quickly and completely a tablet breaks down in the body to be absorbed into the bloodstream. The FDA has categorized this recall as Class II, a designation meaning that while use of the affected product could lead to temporary or medically reversible adverse health outcomes, the risk of severe, long-term harm is extremely low. The only affected lot is Diovan 160 mg with lot number AV5913C, which has an expiration date of June 20, 2027. For patients holding this specific lot, regulators advise against disposing of the medication in regular household trash; instead, unused doses must be returned to the original dispensing pharmacy or the wholesale distributor that supplied the product. Critically, patients currently using Diovan are warned against abruptly stopping their medication without consulting a healthcare provider, as sudden discontinuation of blood pressure or heart failure treatment can create serious avoidable health risks.

    In a second separate recall, the Department of Pharmaceutical Services has announced a Category II Level 2 withdrawal for multiple batches of Atorstan (atorvastatin) 10 mg and 20 mg tablets manufactured by Cyprus-based drugmaker Remedica. All affected batches remain within their approved shelf life and have already entered the local supply chain. The recall was launched after routine stability testing at the manufacturing facility identified certain out-of-specification results that failed to meet regulatory quality standards. Regulators emphasize that based on current data, there is no elevated risk to patient safety from these batches, but the recall was ordered as a proactive precautionary measure to uphold patient safety standards and maintain regulatory compliance. The affected batches are: Atorstan 10 mg (lot 129702, exp April 17, 2028; lot 125293, exp July 23, 2027), and Atorstan 20 mg (lot 123164, exp April 3, 2027; lot 128946, exp December 18, 2027; lot 129730, exp April 17, 2028). Patients holding any of these batches are instructed to return the product to the original point of purchase no later than September 4, 2026. As with the Diovan recall, patients currently taking atorvastatin (a common cholesterol-lowering medication) should not stop treatment without first consulting their doctor or pharmacist, who can provide alternative supplies or adjust treatment plans as needed.

    The third recall is a voluntary withdrawal of four lots of Cetirizine Hydrochloride 5 mg tablets, a widely used over-the-counter and prescription antihistamine for managing allergy symptoms, initiated by Unique Pharmaceutical Laboratories, a division of India-based J.B. Chemicals & Pharmaceuticals Ltd. The recall was launched after a consumer product complaint reported visible red dots and discoloration on tablets from the affected lots, prompting an internal manufacturer investigation that revealed potential cross-contamination with ranitidine, another common medication. Each affected product is packaged in 100-tablet bottles distributed by Rising Pharma Holdings Inc., with lot numbers GY825029, GY825030, GY825031, and GY825032, all expiring in October 2028. The manufacturer notes that for patients with a known hypersensitivity to ranitidine, exposure to contaminated tablets could trigger severe allergic reactions including life-threatening anaphylaxis. To date, no adverse events linked to these contaminated lots have been reported by the manufacturer. Regulators advise patients to immediately stop using any affected lots, return the product to the point of purchase, and contact a healthcare provider if they have experienced any unexplained adverse health effects after using the medication. For specific inquiries about the cetirizine recall, consumers can contact Rising Pharma Holdings Inc. between 8:00 a.m. and 5:00 p.m. EST Monday through Friday.

    In closing its public alert, the Department of Pharmaceutical Services has urged Antigua and Barbuda residents not to panic over the recalls, but to take the necessary precautions seriously. All holders of the medications listed are encouraged to carefully check product labels to confirm name, dosage strength, and lot number, and return any affected products to the appropriate dispensing or supply entity. The department also called on all pharmacies, wholesalers, distributors, and healthcare providers across the country to immediately conduct full inventory reviews, identify any recalled products, and remove them from circulation immediately to prevent further distribution. The Ministry of Health reaffirmed its ongoing commitment to protecting the health and well-being of all Antigua and Barbuda residents, noting that it will continue to closely monitor the recall process and release updated information to the public as new details become available.

  • Identity and Values

    Identity and Values

    Grenada’s modern healthcare system carries the unresolvable imprints of three distinct historical periods, each bringing its own ideological framework that continues to shape access, equity, and patient outcomes today, according to a commentary from Dr. Ishma Harford, a Grenadian medical doctor and Commonwealth Scholar focused on health policy.

    The first foundational layer dates back to Grenada’s independence, when the country inherited a colonial-era healthcare model. Unlike modern frameworks that frame health as a fundamental human right tied to individual dignity, this colonial system treated population health solely as an input for economic production: its only goal was to maintain a sufficiently functional labor force to drive resource extraction and output, with no regard for holistic patient well-being.

    The second transformative shift came during the leadership of Maurice Bishop, when a socialist-influenced revolution upended the old colonial order. For the first time in Grenada’s history, the new administration formally enshrined healthcare as an inalienable right for all citizens, centering its reforms on expanding system capacity, guaranteeing equal access, and universal coverage. The revolution’s government rolled out an aggressive buildout of community clinics across the country, nearly doubled the size of the healthcare workforce and deployed these new providers directly into underserved local communities, and established free universal care as a core governing principle. Unfortunately, the 1983 collapse of the revolutionary government cut this transformative reform effort short before it could reach its full potential.

    The third and most recent ideological influence arrived from Western-aligned market-oriented policy frameworks. Just two months before the revolution fell, in August 1983, Grenada entered into a funding arrangement with the International Monetary Fund (IMF) to access much-needed foreign capital. After the revolution ended, the interim government scrapped the original agreement in January 1984, but a new market-focused direction soon took its place.

    U.S. economic aid arrived alongside deployed U.S. troops, pushing Grenada to become the world’s highest per capita recipient of American economic assistance at the time. Under this new direction, state-owned enterprises and healthcare cooperatives were sold off to private investors, and tax and investment regulations were rewritten to prioritize the interests of foreign capital. By 1992, this shift formalized into a full structural adjustment program led by the principles of the Washington Consensus, with large-scale privatization as its central policy pillar.

    The long-term outcome of this layered, uncoordinated evolution is a healthcare system that systematically disadvantages patients. While not identical to the U.S. model, it shares core structural traits: a largely unregulated, profit-driven private healthcare sector that operates alongside an underfunded, overstretched public system. The U.S. system itself has consistently ranked last among comparable high-income nations in global healthcare assessments from the Commonwealth Fund, where high out-of-pocket patient costs threaten the financial stability and quality of life for millions. In Grenada, this dynamic mirrors that reality: 2021 data shows that more than half of all national health spending is paid directly out of patients’ own pockets.

    Today, Grenada’s healthcare system has stabilized in its mixed public-private form, but it has never reconciled the competing ideological values of its three historical origins. These unresolved tensions are clearly visible in the unequal access and poor patient outcomes that the country currently faces. The nation now stands on the brink of a new wave of systemic change, with ongoing initiatives including Project Polaris, new cross-sector collaborations, digital technology integration, and promised restructuring under the new Hospitals Act all holding significant transformative potential. However, Harford warns that pushing forward with reform without addressing the system’s unsettled core identity risks scaling up pre-existing failures, or even embedding harmful inequalities deeper into the system’s structure.

    To build a more equitable and effective healthcare system for future generations, Harford argues reform must be anchored by explicit, deliberate core values: equity, quality, patient safety, and operational efficiency top the list. While it is unrealistic to embed every desirable value into a reform effort all at once, progress requires starting with a small set of intentional principles that grow alongside the evolving system. This shared commitment cannot be imposed top-down; it must be developed collaboratively and consciously by all system stakeholders, from patients and frontline healthcare providers to policymakers and system administrators.

    This foundational work is not flashy, Harford notes, and it does not deliver quick, politically marketable legacies. It is slow, demanding work that requires shifting deep-seated cultural norms, long-held ways of thinking, and established institutional practices. That is precisely why this work has been deferred for decades, leaving each era’s values to be set solely by the ruling power of the time with no effort to reconcile competing priorities.

    Reform is already underway in Grenada, and decisions that will define the future of the country’s healthcare system are being made every day. Without intentional action, the system’s unaddressed historical values will continue on their current path, reproducing the inequitable outcomes that define Grenada’s healthcare today. But if stakeholders choose to act deliberately, the nation can rebuild its healthcare foundation on the values that Grenadian patients not only demand, but deserve.

    This article is part of *The Health Imperative*, a politically neutral educational column focused on health, healthcare systems, and their broader societal impacts. Dr. Harford is currently pursuing a master’s degree in Health Analysis, Policy and Management as a Commonwealth Scholar. NOW Grenada notes that it is not responsible for the opinions and statements presented by contributing authors.

  • Ebola-uitbraak in DR Congo wordt dodelijkste in de geschiedenis van het land

    Ebola-uitbraak in DR Congo wordt dodelijkste in de geschiedenis van het land

    The Democratic Republic of the Congo (DRC) is currently grappling with its deadliest Ebola outbreak on record, with the death toll climbing to 2,325 as of mid-August, according to the country’s National Institute of Public Health. This figure surpasses the 2,299 fatalities recorded during the 2018–2020 outbreak, the previous deadliest event in the nation’s history of Ebola responses.

    Confirmed infections have now reached 4,945 total cases, with 101 new positive detections reported in just the 24-hour period preceding the institute’s latest update. Tom Fletcher, the United Nations Humanitarian Coordinator, emphasized that this outbreak is spreading faster than any previous Ebola event recorded in the DRC. He warned that urgent, scaled-up action and global solidarity are critical to bringing the virus under control before it becomes completely unmanageable.

    This outbreak marks the 17th recorded Ebola event in the DRC, and it first outpaced the 2018–2020 outbreak in total case counts back in late July. World Health Organization (WHO) Director-General Tedros Adhanom Ghebreyesus issued a stark warning this week: if transmission continues at its current rate, the outbreak could overtake the devastating 2014–2016 West African Ebola crisis, which killed more than 11,000 people across the region.

    A unique set of challenges is amplifying the severity of this outbreak. Unlike previous large Ebola events in the DRC, the current outbreak is caused by the Bundibugyo strain of the ebolavirus, for which no fully approved vaccines or targeted treatments currently exist. Response efforts are further hampered by systemic barriers: the DRC’s fragile public health infrastructure, the remote, hard-to-reach location of many affected communities, and ongoing armed conflict along the country’s borders with South Sudan, Uganda and Rwanda all slow coordinated containment work.

    The DRC has faced recurrent Ebola outbreaks for decades, a pattern partially driven by its geographic location within the Congo Basin, where the virus is naturally hosted in wild animal populations, particularly fruit bats. Spillover to humans most often occurs after contact with infected wild animals, followed by secondary human-to-human transmission. Long-standing structural issues including persistent political instability, widespread poverty, and limited access to basic healthcare have also made it far harder to curb outbreaks once they emerge.

    Alarming new data shows the case fatality rate has surged from roughly 20% in June to 47% today, meaning nearly half of all confirmed Ebola patients are now dying from the virus. This trend runs directly counter to the typical pattern of Ebola outbreaks, where fatality rates usually fall as contact tracing improves and patients receive care earlier in the course of infection.

    Thomas Parisch, a senior official with Doctors Without Borders (MSF), explained the root of this rising mortality: most cases are only detected far too late, often after the patient has already died in the community, leaving no window for life-saving intervention.

    Right now, public health researchers are conducting clinical trials of several experimental vaccines and targeted therapies for the Bundibugyo strain, while health authorities are also investigating whether existing Ebola treatments developed for other strains can offer any cross-protection. As of the latest update, evidence of that cross-protection remains limited exclusively to preclinical animal studies, with no conclusive human trial data available yet.

  • Dengue Threat Grows as Stagnant Water Builds Up

    Dengue Threat Grows as Stagnant Water Builds Up

    As the 2026 rainy season brings lower temperatures to Belize, it is simultaneously spurring a growing public health threat: a sharp increase in dengue fever risk fueled by expanding pools of stagnant water, the ideal breeding ground for the Aedes aegypti mosquitoes that carry the virus.

    In a public advisory released on August 17, Belize’s Ministry of Health and Wellness has issued an urgent call to action for all residents across the Belize District to proactively inspect their properties, workplaces and shared community spaces for any collections of standing water that could support mosquito breeding.

    Health authorities stress that dengue fever presents a wide spectrum of severity, ranging from mild, flu-like discomfort to life-threatening critical illness, with fatal outcomes recorded in a number of cases. Recognizable symptoms of the disease include sudden high fever, intense headaches, sharp pain behind the eyes, widespread muscle and joint soreness, skin rashes, abnormal bleeding, and labored breathing. The Ministry emphasizes that anyone who develops these symptoms should seek immediate professional medical care to reduce the risk of complications.

    To help the public limit mosquito exposure and breeding, public health officials have outlined a series of simple, actionable prevention steps. Residents are encouraged to regularly empty or securely cover any outdoor containers that can collect rainwater, clear clogged drains and overgrown yard debris, dispose of waste items that hold standing water such as old tires, discarded bottles and aluminum cans, use EPA-approved mosquito repellent consistently, wear long-sleeved clothing when spending time outdoors, and ensure all doors and windows have intact, properly fitted mesh screens to keep mosquitoes out of living spaces.

    The Ministry underscored that successful dengue prevention cannot be achieved by public health authorities alone: it is a shared collective responsibility that requires active participation from every community member. Government health teams continue to collaborate closely with local community leaders and municipal authorities to expand disease surveillance and scale up targeted vector control measures across at-risk areas.

  • Sickle Cell Unit Opens at Old Holberton Hospital

    Sickle Cell Unit Opens at Old Holberton Hospital

    Antigua and Barbuda has marked a major milestone in expanding specialized care for individuals affected by sickle cell disease, with the official opening of a dedicated Sickle Cell Unit on the campus of the Old Holberton Hospital. Starting Wednesday, August 19, the new facility will open its doors to patients, bringing much-needed targeted care closer to local communities that have long faced gaps in access to sickle cell management.

    Helmed by hematology specialist Dr. Veena Vignarajah, the newly launched unit is designed to address the full spectrum of needs for people living with the genetic blood disorder. Beyond providing urgent, rapid intervention for acute pain crises — one of the most common and debilitating complications of sickle cell disease — the facility will also deliver comprehensive ongoing care. This includes regular wellness monitoring to track long-term health outcomes, customized patient education to help individuals manage their condition at home, and dedicated psychosocial support to address the mental and emotional toll that chronic illness can place on patients and their loved ones.

    A key part of the unit’s public health mandate is integrating its services with Antigua and Barbuda’s national newborn screening program, a strategic move designed to prioritize early intervention. By collaborating closely with the screening initiative, the unit will enable earlier detection of sickle cell disease in infants, ensuring that affected children and their families can access critical care, resources, and support from the earliest stages of life. This early intervention approach is widely recognized by global health experts to improve long-term health outcomes and reduce the risk of life-threatening complications for people born with the condition.

    Health officials across the country have welcomed the launch as a critical step forward in strengthening the nation’s public health infrastructure, filling a long-standing gap in specialized care for the sickle cell community. For patients and families across Antigua and Barbuda, the new facility means they no longer need to travel abroad for routine or urgent sickle cell care, reducing financial and logistical burdens while improving access to life-sustaining treatment.

  • Antigua and Barbuda Recalls Three Pharmaceutical Products Over Quality and Contamination Concerns

    Antigua and Barbuda Recalls Three Pharmaceutical Products Over Quality and Contamination Concerns

    The Department of Pharmaceutical Services under Antigua and Barbuda’s Ministry of Health, Wellness, the Environment and Civil Service Affairs has issued a public notification alerting consumers, healthcare providers, pharmacies, drug wholesalers, distributors and other industry stakeholders to a coordinated recall of three separate lines of pharmaceutical products that have entered distribution channels across the island nation.

    The first recall centers on a specific lot of Novartis’ Diovan 160 mg tablets, a widely prescribed valsartan-based medication classified as an angiotensin II receptor blocker used to manage high blood pressure and heart failure. The voluntary recall was first announced by the U.S. Food and Drug Administration (FDA) on August 4, 2026, after quality testing revealed the product failed to meet required dissolution specifications. This means the tablet does not break down at the expected rate in the body, preventing proper absorption of the active ingredient. The FDA has categorized this recall as Class II, a designation indicating that while temporary or reversible adverse health effects are a possible outcome of use, the risk of serious, life-threatening harm is extremely low. The only affected batch carries lot number AV5913C with an expiration date of June 20, 2027.

    Regulators have issued clear guidance for patients holding this specific Diovan lot: the recalled medication should not be thrown away with regular household trash. Instead, any unused portions must be returned to the original dispensing pharmacy or the wholesale distributor that supplied the product. Crucially, patients are warned not to discontinue use of their blood pressure or heart failure medication without first consulting a prescribing doctor or pharmacist, as abrupt stopping of these treatments can create significant, immediate health risks.

    A second recall, classified as Category II Level 2, covers specific batches of 10 mg and 20 mg Atorstan (atorvastatin) tablets manufactured by Cyprus-based drug producer Remedica. Atorvastatin is a commonly prescribed statin used to lower LDL cholesterol and reduce cardiovascular disease risk. All affected batches remain within their approved shelf life and have been distributed across Antigua and Barbuda. The recall was launched after ongoing stability testing at the manufacturing facility returned out-of-specification results for the product. While current risk assessments have found no indication of severe danger to patient safety, regulators ordered the recall as a precautionary measure to uphold regulatory compliance and protect public health.

    The affected Atorstan batches are: 129702 (10 mg, exp. April 17, 2028), 125293 (10 mg, exp. July 23, 2027), 123164 (20 mg, exp. April 3, 2027), 128946 (20 mg, exp. December 18, 2027), and 129730 (20 mg, exp. April 17, 2028). Patients holding any of these batches are required to return the product to the point of purchase by the September 4, 2026 deadline. As with Diovan, patients are advised not to stop taking atorvastatin without consulting a healthcare provider, who can supply an alternative product or adjust the treatment plan if needed.

    The third recall involves four lots of 5 mg Cetirizine Hydrochloride USP 100-tablet bottles, a widely used over-the-counter and prescription antihistamine for treating allergy symptoms. The voluntary recall was initiated by manufacturer Unique Pharmaceutical Laboratories, a division of India-based J.B. Chemicals & Pharmaceuticals Ltd., which distributes the product in the region through Rising Pharma Holdings Inc. The safety issue was first flagged after a consumer complaint reported unexplained red dots and discoloration on tablet surfaces. Further investigation found potential cross-contamination with ranitidine, a histamine-2 blocker previously used to treat acid reflux.

    Manufacturers warn that for patients with a confirmed hypersensitivity to ranitidine, exposure to contaminated cetirizine could trigger severe allergic reactions, including life-threatening anaphylaxis. As of the recall announcement, the manufacturer has not received any reports of adverse events linked to the affected lots. The affected batches, all with an October 2028 expiration date, carry lot codes GY825029, GY825030, GY825031, and GY825032. Consumers are instructed to immediately stop using any cetirizine from these lots, return the product to the point of purchase, and contact a healthcare provider if they have experienced any unexplained health issues after using the product. Medical inquiries about the recall can be directed to Rising Pharma Holdings Inc. during regular business hours (8 a.m. to 5 p.m. EST, Monday through Friday).

    In closing, the Department of Pharmaceutical Services stressed that while the public does not need to panic, it is critical that all stakeholders take the recall notices seriously. Consumers are encouraged to carefully check the lot numbers, product names, and dosage strengths of any medications they hold at home, and return confirmed affected products to the appropriate dispensing or distribution point immediately. The department has also ordered all pharmacies, wholesalers, distributors, and healthcare providers to conduct immediate inventory checks to pull all recalled products from circulation, preventing further distribution to patients.

    The Ministry of Health reaffirmed its ongoing commitment to protecting the health and well-being of all residents of Antigua and Barbuda, noting that it will continue to monitor the unfolding recall situation and update the public with any new information as it becomes available.

  • PAHO launches toolkit to prevent bullying and cyberbullying among children and adolescents

    PAHO launches toolkit to prevent bullying and cyberbullying among children and adolescents

    Millions of children and adolescents across Latin America and the Caribbean face the persistent harm of bullying and cyberbullying, a pervasive form of peer violence that leaves lasting damage to physical, mental and emotional well-being. To address this growing public health crisis, the Pan American Health Organization (PAHO) has introduced a groundbreaking new resource: the *What Works to Prevent Bullying and Cyberbullying of Children and Adolescents in the Americas* toolkit. This comprehensive guide consolidates verified research, actionable policy recommendations, and practical on-the-ground tools to help stakeholders across sectors prevent these forms of violence and deliver targeted support to affected young people.

    The toolkit opens by mapping the scope of the crisis across the region, laying out the profound harm bullying inflicts on young populations, and detailing evidence-backed intervention strategies that have been proven effective. Drawing on cross-sector research from public health, education, and social protection systems, the resource specifically highlights the underrecognized critical role that health services play in early detection, holistic care, and ongoing support for youth impacted by bullying and cyberbullying.

    “Bullying during childhood and adolescence is a form of peer violence that can have significant consequences for physical, sexual, mental, and emotional health,” explained Britta Baer, PAHO Regional Advisor on Violence and Injury Prevention and co-author of the new toolkit. “The good news is that it can be prevented. We have evidence on what works, and this toolkit aims to make that evidence accessible to decision-makers, people who work with adolescents, and those who support their development.”

    Regional data compiled in the toolkit underscores the scale of the problem: roughly one in four 13 to 17-year-olds across Latin America and the Caribbean report experiencing in-person bullying at school in the past 30 days, with prevalence varying across subregions. Central America records a 23% bullying prevalence rate among students, while South America sees that rate climb to 30%.

    Bullying manifests in multiple overlapping forms, including physical, verbal, sexual, and social aggression, with distinct patterns by gender. Physical bullying is more commonly reported among boys, while girls are disproportionately impacted by social and sexual bullying, with differing associated harms and rates of help-seeking.

    Cyberbullying, the digital variant of the violence, affects between 7% and 27% of children and adolescents across the region over a 12-month period, with higher rates recorded among girls. Unlike traditional in-person bullying, cyberbullying can invade a young person’s space at any time of day, spread to massive online audiences in seconds, and leave permanent digital traces. The anonymity afforded to perpetrators online also amplifies harm and makes the abuse far harder to regulate and stop.

    PAHO stresses that cyberbullying rarely exists in a vacuum. It often mirrors, amplifies, or extends patterns of violence that already occur offline, most frequently in school settings. It also commonly overlaps with other forms of digital abuse, including non-consensual sharing of private information, identity theft, image-based harassment, and other forms of coercive online control.

    Recognized as a core public health priority, bullying in all its forms is a major determinant of long-term health and well-being for young people. Both in-person and online bullying severely disrupt healthy development, and are linked to sharply increased risks of depression, anxiety, traumatic stress, social isolation, sleep disorders, self-harm, suicidal ideation, and suicide attempts, alongside negative outcomes for academic performance and social integration. Research compiled in the toolkit confirms that young people who experience bullying are far more likely to report loneliness, sleep disruption, and suicidal thoughts than peers who have not faced abuse.

    Bullying also damages physical, sexual, and reproductive health, causing everything from acute injuries and chronic psychosomatic pain to increased risk of sexual coercion. These far-reaching harms demonstrate that addressing bullying cannot be left solely to school systems; coordinated engagement from public health systems is essential to meet the full scope of young people’s needs.

    The toolkit further warns that different forms of violence often overlap and reinforce one another: abuse may begin online before moving to in-person interactions, or start offline and be amplified through digital platforms. This makes early intervention critical to breaking cycles of violence and reducing the risk of long-term harm across a young person’s life.

    To support early detection, the guide outlines key warning signs that caregivers and health providers can watch for: sudden shifts in behavior, increased anxiety or irritability, social withdrawal, unexplained injuries, and new reluctance to attend school. For cyberbullying specifically, additional red flags include abrupt changes in behavior during or immediately after digital device use, quickly closing screens when adults approach, and refusal to discuss online activities.

    PAHO identifies health services as a critical first point of contact for recognizing these warning signs, delivering initial support, and connecting young people to specialized care when needed. The toolkit recommends that health care workers integrate questions about school climate and digital experiences into routine youth check-ups, proactively identify warning signs, assess potential mental health impacts, and provide immediate support to affected youth. It also emphasizes the importance of supporting families to foster safe digital habits and coordinating closely with schools and other sectors to deliver a cohesive, comprehensive response.

    “The most important thing is for children and adolescents to know that bullying and cyberbullying are never acceptable and that they do not have to face them alone,” Baer noted. “Seeking help from a trusted adult and using available reporting mechanisms can make a real difference.”

    Addressing bullying effectively requires coordinated action across multiple sectors and stakeholder groups, with meaningful youth participation at the center of successful strategies, PAHO emphasizes. The toolkit highlights the value of strengthening peer support networks and building young people’s social and emotional skills as key protective factors. It also encourages parents and caregivers to maintain open lines of communication with their children, stay alert for warning signs of abuse, coordinate with schools when concerns arise, and set clear, collaborative agreements for safe and responsible internet and mobile device use.

    Public health, education, and government agencies at all levels are called on to collaborate to develop and roll out evidence-based violence prevention responses. The guide also underscores the critical responsibility of the private sector, particularly digital platform operators, to work alongside governments and communities to embed safety and protection into product design from the earliest stages.

    The new toolkit is part of PAHO’s longstanding ongoing work to strengthen prevention of violence against children and adolescents, and to support member states in breaking intergenerational cycles of violence through accessible, evidence-driven resources.

  • Dengue Cases Expected to Rise as Rainy Season Sets In

    Dengue Cases Expected to Rise as Rainy Season Sets In

    As daily rainfall becomes consistent across Belize, public health officials have issued an urgent warning to residents: the warm, wet conditions created by the rainy season create the perfect environment for dengue virus transmission, and case numbers are projected to climb in the coming weeks.

    The Ministry of Health and Wellness is leading a public outreach campaign urging all Belizeans to take proactive steps to eliminate mosquito breeding grounds on their personal property before a preventable pest problem turns into a widespread public health crisis.

    Dengue, a viral infection spread exclusively by female Aedes aegypti mosquitoes, relies on standing water to complete the insect’s reproductive cycle. Public health experts note that these mosquitoes can breed in even tiny volumes of trapped water – as little as the amount held in a discarded bottle cap. Common breeding sites around residential properties include unused old tires, empty aluminum cans, clogged storm drains that do not drain properly after rainfall, and overgrown, unkempt yards that collect standing water.

    Symptoms of a dengue infection vary widely from person to person. Most patients experience mild to moderate reactions that include high fever, intense persistent headaches, severe joint and muscle pain, and characteristic skin rashes. In severe, untreated cases, however, the infection can progress to life-threatening complications including internal bleeding and acute respiratory distress. Health officials emphasize that anyone who develops these symptoms should seek immediate professional medical care, rather than delaying treatment to see if symptoms resolve on their own.

    Beyond eliminating breeding sites, the Ministry of Health has outlined a set of simple, everyday precautions residents can take to reduce their risk of being bitten. These include regularly applying CDC-recommended insect repellent, wearing long-sleeved clothing and long pants during the mosquito’s peak feeding hours at dawn and dusk, and ensuring windows and doors have intact screens to block mosquitoes from entering indoor living spaces.

    Health authorities confirmed that they are already working in close coordination with municipal governments, local community organizations, and other stakeholders to expand nationwide dengue surveillance and implement large-scale mosquito control measures across the country. Despite these ongoing systemic efforts, officials stress that individual action remains the most critical line of defense, repeating their core public appeal: every Belizean should take time today to check their yard for standing water.

  • GB mom overcomes stage two breast cancer

    GB mom overcomes stage two breast cancer

    For 30-year-old Desire Sands of Grand Bahama, the past year has been defined by parallel grief and grit: just seven months after laying her mother to rest following a breast cancer battle, she received a diagnosis of stage two breast cancer herself. Now, after months of grueling treatment, Sands is celebrating the milestone of being declared cancer-free, a win she calls nothing short of a second chance at life.

    When Sands received her diagnosis in April 2025, her daily routine shifted dramatically. What had been days spent playing with her three-year-old young son turned into a grueling cycle of regular trips from Grand Bahama to New Providence, where she underwent chemotherapy appointments at Princess Margaret Hospital’s Oncology Clinic. Through every step of the treatment process, she carried the memory of her mother, who had lost her own fight with the same genetic-linked disease just months prior.

    The life-changing confirmation of her remission came on August 10, when a close friend accompanied her to a routine appointment with her oncologist on Grand Bahama. As her care provider reviewed her pathology reports and blood work, he delivered the news Sands had waited months to hear: she was officially cancer-free. “My initial reaction was emotional because that’s something I’ve been waiting to hear,” Sands shared in an interview. “I’m still processing it honestly, and I was excited to give the good news to the same persons I gave the bad news to when I first got diagnosed.”

    Sands says the clean bill of health feels like a new beginning, an opportunity to live with even more intentionality than she did before her diagnosis. Her oncologist echoed that sentiment, encouraging her to pursue new goals from going back to school to learning a new skill, reminding her it was finally time to embrace the next chapter.

    But Sands’ road to remission was far from easy. A person living with sickle cell disease, she faced amplified complications during her final four rounds of chemotherapy. The powerful treatment triggered severe joint pain that was hard to distinguish from a sickle cell crisis, leaving her struggling to cope with unrelenting discomfort. She was admitted to hospital twice during this period, and at one point required three blood transfusions to stabilize her health.

    Even at her lowest points, however, Sands never allowed fear of death to take root. “I never allowed negative thoughts to overwhelm me,” she explained. “Anytime something happened I just took it as “I’m not going to rush my process” even though I wanted to be done quickly.”

    One of the hardest parts of her journey, she said, was maintaining a sense of strength for her young son, who often noticed when she was fatigued or unwell. Sands made a deliberate effort to explain her illness to her son in age-appropriate terms, and he soon developed a gentle understanding of what she was going through. After treatments, he would kiss her treatment port and check in to ask how she was feeling. That small, consistent support kept her going, she said: “I know I needed to keep going for him because he saw me at my lows and I wanted him to see the good too.”

    Sands credits her unwavering faith in God as a core source of strength throughout her battle, alongside the support of friends and family. Cancer has touched multiple generations of her family, and even as she grieved her mother’s death while fighting her own diagnosis, she said her mother’s memory remained a constant inspiration.

    Now stepping into what she calls her new chapter, Sands wants to share a message of hope with other women navigating breast cancer treatment. Too often, she said, society frames a cancer diagnosis as an automatic death sentence, and doesn’t celebrate enough the stories of people who fight and win. But that narrative doesn’t have to hold, she said: “Cancer isn’t a death sentence. Once you lean on God’s strength and do as your doctor says your journey will be a good one.”